Every Body, But Not Every System: Where Sexual Health Infrastructure Is Failing
Published in Microbiology, General & Internal Medicine, and Public Health
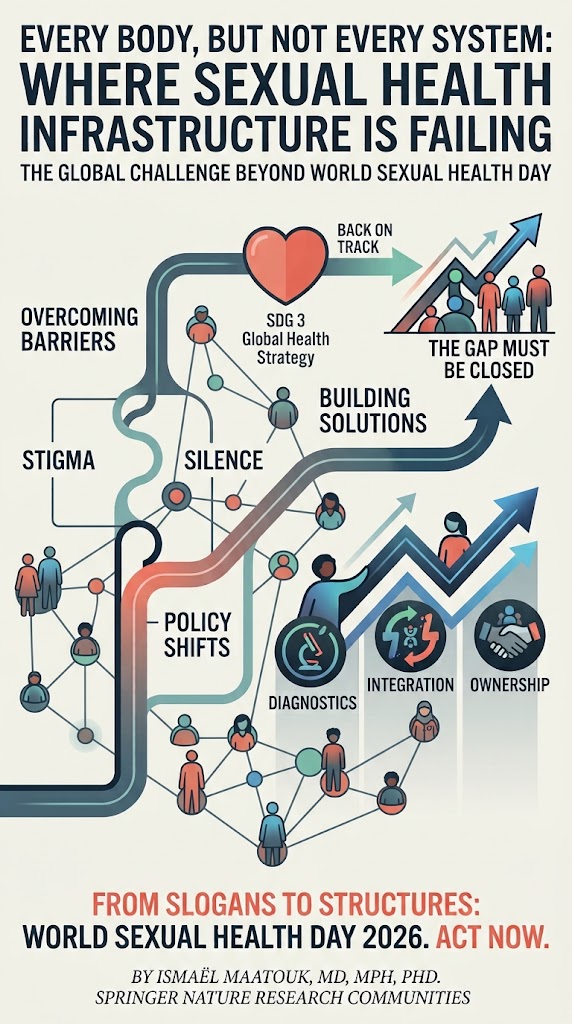



World Sexual Health Day 2026 carries a theme that sounds inclusive: "Every Body." Five dimensions follow from it: the personal, the relational, the institutional, the cultural, and the political. The first two depend on the last three. And it is the last three that are now under direct threat.
When I was at WHO headquarters, I coordinated the development of the WHO Consolidated Operational Handbook on Sexually Transmitted Infections, released in February 2026. The handbook brings together, for the first time, all WHO normative and operational guidance on STI prevention, diagnosis, treatment, surveillance, and service delivery published between 2016 and 2025. It exists because the global STI response has never matched the scale of the problem. More than one million new curable STIs are acquired every day. Syphilis infections rose to an estimated eight million globally in 2022, with about 700,000 cases of congenital syphilis. These numbers are not new. The failure to act on them is not new either.
The systems we built are not enough
The WHO Global Health Sector Strategy on STIs sets a target: reduce gonorrhoea and syphilis infections by 90% by 2030 (SDG 3). Most countries are not on track. Many have no national STI strategy at all. Those that do often lack the budget, the workforce, or the political will to put it into operation.
Start with diagnostics. Most low- and middle-income countries still use syndromic management. Clinicians treat symptoms without a confirmed pathogen. Point-of-care tests for syphilis exist but reach only a fraction of the population that needs them. For Mycoplasma genitalium, a pathogen with macrolide resistance above 60% in parts of Europe, most clinics cannot test at all. The operational handbook introduces the STI prevention and care cascade as a framework to map where people fall out of the system. In most settings, they fall out early.
Then look at services. STI care, HIV treatment, and sexual and reproductive health remain separate in most countries. Patients move between departments that do not share records, referrals, or accountability. The handbook provides package-based guidance to integrate these services within primary health care. But integration needs a national decision, national financing, and national ownership. External donors cannot build it. Countries must.
Stigma and silence are structural failures, not cultural inevitabilities
STIs remain taboo in nearly every setting, including the most advanced. Patients delay care because of shame. Clinicians avoid sexual history-taking because they lack training or comfort. Public health campaigns on STIs are rare compared to those on diabetes, cancer, or even HIV. Advocacy is weak because few political leaders will attach their name to a sexually transmitted infection.
This silence has a cost. Without public pressure, STI programmes stay underfunded. Without advocacy, national STI responses stay low on the political agenda. Without open conversation, the populations most affected (sex workers, men who have sex with men, adolescents, people in conflict settings) remain invisible to the systems that are supposed to serve them.
"Every Body" cannot be a theme for one day in September if the rest of the year these bodies do not appear in national health budgets, training curricula, or parliamentary debates.
When policy environments shift, health systems pay the price
Sexual health infrastructure is shaped by policy decisions that often happen far from clinics. When foreign assistance decreases, HIV and STI service sites close. A Lancet analysis of 133 countries found that two decades of global health programming prevented 91.8 million deaths. The same analysis projects 14 million additional deaths by 2030 if current funding reductions continue. In Pakistan, 331 children were infected with HIV at a single hospital through reused needles. These are failures of financing, governance, and oversight.
Vaccine programmes face similar pressures. When immunization policy follows political debate rather than scientific evidence, coverage drops. The history of vaccine programme disruptions across multiple countries shows how quickly public trust, once lost, takes a generation to rebuild.
The populations that carry the cost are always the same: women, children, sex workers, men who have sex with men, people in conflict zones, people in poverty. Sexual health does not exist in isolation from these broader policy shifts. Every disruption in global health financing or evidence-based decision-making reaches STI services, often first.
What "Every Body" demands
If the WSHD 2026 theme is more than a slogan, it must translate into structural demands. Countries must own their national STI responses with domestic financing, not depend on external donors whose priorities shift. Surveillance systems must detect resistance before it becomes untreatable. Diagnostic capacity must reach beyond referral hospitals. Vaccine programmes must follow scientific evidence. Service models must integrate STI, HIV, and reproductive health care so that patients do not fall between them. Training pipelines must produce providers who can meet patients without judgment.
The SDG 3 targets on STIs are five years away. Most countries will not meet them. The question is whether we will name the reasons (underfunding, stigma, weak advocacy, fragile national ownership) or continue to write declarations that no system is built to deliver.
On September 4, World Sexual Health Day asks us to close that gap. The operational handbook exists. The evidence exists. What remains is the institutional will to act on them.
Ismaël Maatouk, MD, MPH, PhD, is a Professor of Dermatology and STIs at the University of Balamand (Lebanon), and a global sexual health physician. He is an Editorial Board member of BMC Global and Public Health.

Follow the Topic
-
BMC Global and Public Health
An open access, transparent peer review journal publishing outstanding and influential research and opinion of broad interest to all professional communities involved in global and public health research, policy-making, implementation and delivery worldwide.

Related Collections
With Collections, you can get published faster and increase your visibility.
Environmental exposure, maternal health and child health
BMC Global and Public Health is pleased to announce a call for papers for our upcoming collection entitled Environmental exposure, maternal health and child health, guest edited by Dr. Nuria Güil from the Barcelona Institute for Global Health, Spain, Dr. Pengfei Guo from University of South Carolina, USA and Dr. Wei Li from Yale University, USA. The aim of the collection is to capture global efforts and novel approaches in this multi-disciplinary area. Maternal and child health is a substantial domain of global public health, with outcomes that shape individual well-being and societal development. Pregnancy and early life are periods of heightened biological sensitivity, during which exposures exert lasting effects. Complications such as hypertensive disorders, gestational diabetes, and perinatal mental health challenges, as well as birth and child outcomes including preterm birth, growth restriction, and neurodevelopmental impairment, highlight the need for continued research and intervention to reduce risks and promote health equity.
Environmental exposures are increasingly recognized as critical and modifiable determinants of maternal and child health. Adverse exposures such as ambient air pollution, environmental tobacco or cannabis smoke, contaminated water, pesticides, endocrine disruptors, heavy metals, noise, light pollution, natural disasters, and other emerging pollutants contribute to reproductive and developmental risks, often acting in mixtures and interacting with social or neighborhood determinants. At the same time, positive environmental influences such as access to clean air and water, green space, safe housing, and supportive community environments, have been shown to promote healthier pregnancies, enhance child neurodevelopment, and reduce stress for families. Advancing knowledge of both harmful and protective pathways is essential for developing effective interventions, guiding policy, and addressing environmental challenges that threaten maternal and child health.
We are now inviting the submission of manuscripts of outstanding interest covering the breadth of multi-disciplinary studies, ranging from observational to interventional that are focused on the effect of environmental exposure on maternal and child health. We envision this work to inform future research, conceptual frameworks, intervention development, and policy advancement.
Sample foci of papers include:
- Epidemiological studies on environmental exposures (e.g., air pollutants, per- and polyfluoroalkyl substances, pesticides, heavy metals, plastics, greenspace, noise, climate-related hazards) and maternal, fetal, and child health outcomes
- Environmental tobacco or cannabis secondhand smoke exposure and postpartum physical and mental health on maternal and child health (e.g., postpartum depression and anxiety, maternal sleep and recovery, breastfeeding outcomes, infant respiratory illness and neurodevelopment)
- Population-level insights into contextual pathways and disparities (e.g., social determinants, neighborhood environment, climate vulnerability) that influence reproductive, perinatal, and developmental health outcomes
- Policy, intervention, and prevention strategies to reduce environmental risks and improve maternal and child health globally
- Interactions between environmental exposures and social determinants of health
- Novel data collection/assessment tools (e.g., mixture, exposome, or omics approaches)
This Collection supports and amplifies research related to SDG 3: Good Health and Well-being.
We encourage work from local, regional and global partnerships and collaboration among scientists from multi-disciplinary fields and using multiple methodologies. We ask that authors be attentive to the use of non-stigmatizing/preferred language in their manuscripts as outlined in relevant language guidelines for their respective fields.
All manuscripts submitted to this journal, including those submitted to collections and special issues, are assessed in line with our editorial policies and the journal’s peer-review process. Reviewers and editors are required to declare competing interests and can be excluded from the peer review process if a competing interest exists.
Publishing Model: Open Access
Deadline: Oct 30, 2026
Advanced data-driven analytical frameworks to support and improve policy decisions
BMC Global and Public Health is calling for submissions to our Collection on how the integration of advanced data-driven methods in public health policy is rapidly transforming how we understand and respond to global health challenges. This Collection focuses on the application of innovative statistical modelling, machine learning, and geographic information systems (GIS) to inform health policy decisions. By integrating data from surveys and health records with information on social and environmental determinants, researchers can uncover actionable insights that enhance the effectiveness and efficiency of health interventions across diverse populations.
The relevance of these advanced methodologies is underscored by recent advancements in methods for data collection and analysis, which have enabled researchers to create more precise models for predicting disease outbreaks, evaluating health interventions, and addressing health disparities. As public health continues to confront complex issues such as pandemics and non-communicable diseases, the ability to leverage data-driven strategies becomes increasingly vital for crafting evidence-based policies that are responsive to real-world challenges.
Continued research in this area could lead to groundbreaking methodologies that enhance our understanding of health dynamics and improve public health responses. Future advancements may include the development of real-time data analytics for tracking disease spread, enhanced spatial epidemiological models that account for environmental variables, and improved collaboration between data scientists and public health professionals. By further integrating data science with public health, we can pave the way for more effective interventions and ultimately improve health outcomes globally.
We encourage submissions in the following areas, with a particular interest in studies relevant to low- and middle-income countries (LMICs); however, contributions from all settings are welcome, including:
- Applications of Machine Learning in Public Health
- Spatial Epidemiology and Disease Mapping
- Statistical Modeling for Health Policy Decisions
- GIS in Public Health Decision Making
- Evidence-Based Approaches to Infectious and Non-communicable Diseases
This Collection supports and amplifies research related to SDG 3: Good Health and Well-being.
All manuscripts submitted to this journal, including those submitted to collections and special issues, are assessed in line with our editorial policies and the journal’s peer-review process. Reviewers and editors are required to declare competing interests and can be excluded from the peer review process if a competing interest exists.
Publishing Model: Open Access
Deadline: Nov 14, 2026