Beyond the Prescription Pad: The Unseen Cost of Polypharmacy in Secondary Healthcare
Published in Chemistry



Every day at the pharmacy counter of Offa Specialist Hospital in Kwara State, North-Central Nigeria, a quiet crisis unfolds at the cash register. It starts with the soft rustle of paper—a prescription slip carrying a long, daunting list of life-sustaining medications. Then comes the pause. A patient checks their wallet and makes an impossible choice: Which of these five pills can I afford to take this month?
Behind our newly published study lies a stark reality about the human and economic toll of multi-drug therapy in resource-limited settings. While multi-drug regimens are often clinically necessary for managing chronic conditions, their benefits routinely collide with financial realities where healthcare depends on out-of-pocket spending.
Key Findings from the Field
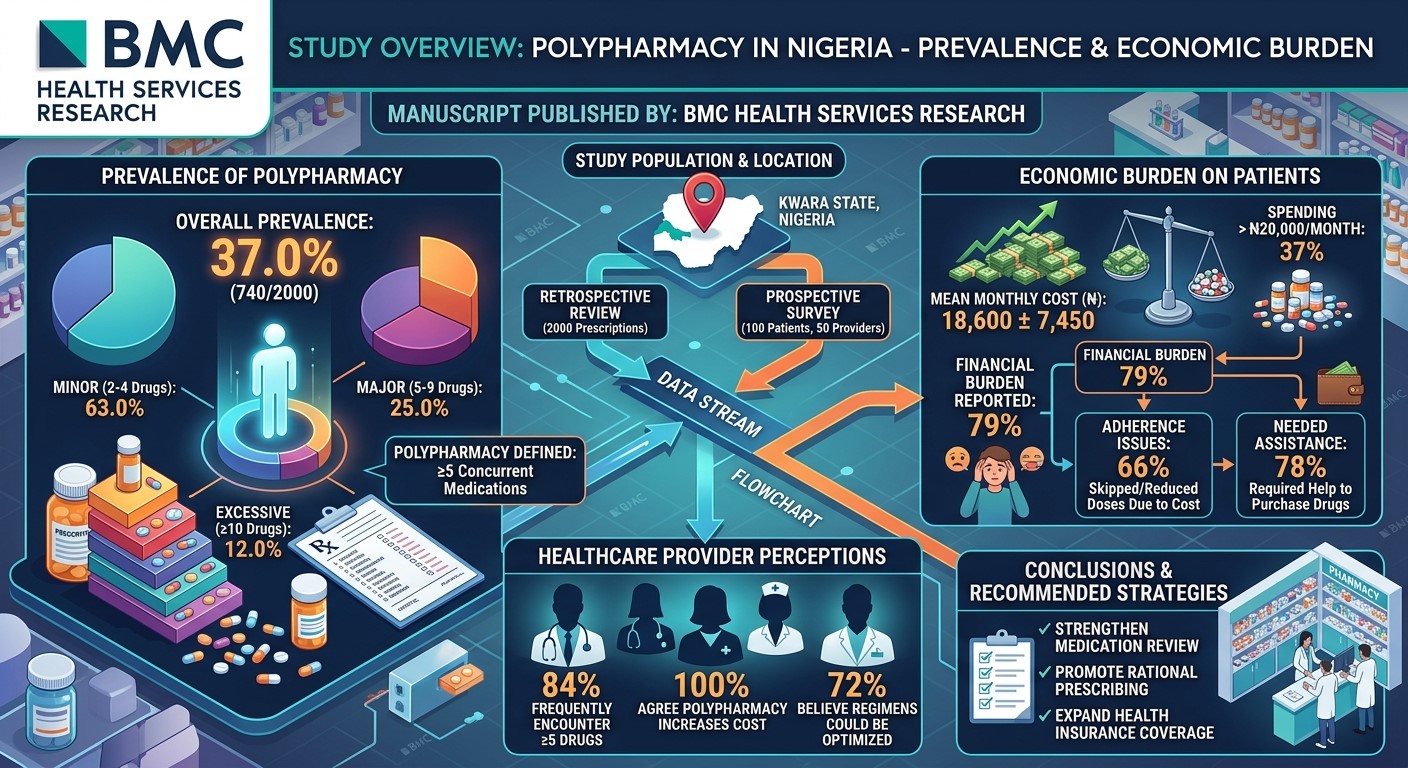
- High Prevalence: Of 2,000 reviewed prescriptions, 0% met the criteria for polypharmacy (≥5 drugs), with 12.0% involving excessive polypharmacy (≥10 drugs).
- Severe Financial Strain: 37% of surveyed patients spend over ₦20,000 monthly on drugs, and 79% report that medication costs pose a significant financial burden.
- Compromised Adherence: 66% of patients admitted to skipping doses, reducing intake, or delaying drug purchases due to cost, while 78% required financial help from family or friends to buy their medicines.
- Provider Consensus: 84% of surveyed healthcare workers frequently encounter polypharmacy, 100% agree it escalates treatment costs, and 72% believe many regimens could be safely streamlined through structured medication reviews.
Moving Toward Solutions
Prescribing a drug is only half the therapeutic equation; ensuring the patient can afford to take it completes the cycle. Mitigating unnecessary polypharmacy in low- and middle-income countries requires three key strategies:
- Routine Medication Reviews: Integrating pharmacist-led audits to optimize drug regimens and initiate safe deprescribing.
- Health Insurance Expansion: Broadening universal coverage to protect households from catastrophic out-of-pocket expenses.
- Multidisciplinary Care: Fostering teamwork among physicians, pharmacists, and clinical pharmacologists to enforce cost-effective, evidence-based prescribing.

Health ROI Architect, BioPolicy Strategist, Pharma Economic Futurist and Therapeutics Pioneer
Follow the Topic
-
BMC Health Services Research
An open access, peer-reviewed journal that considers articles on all aspects of health services research, focusing on digital health, governance, policy, system quality and safety, delivery and access, financing and economics, implementing reform, and the workforce.

Related Collections
With Collections, you can get published faster and increase your visibility.
Patients' knowledge of the indications for their medications
BMC Health Services Research is calling for submissions to our Collection on Patients' knowledge of the indications for their medications.
Understanding the indications for prescribed medications is crucial for patient safety and effective healthcare delivery. Many patients lack adequate knowledge about their medications, which can lead to non-adherence, adverse drug reactions, and suboptimal health outcomes. This Collection invites research that examines the extent of patients' medication knowledge, the factors influencing their understanding, and the implications for healthcare practice. By exploring these aspects, we aim to illuminate the gaps in medication literacy and the importance of patient engagement in their treatment regimens.
Enhancing patients' knowledge of their medications is vital for fostering informed decision-making and promoting adherence to treatment plans. Recent advances in medication counseling, patient education programs, and digital health technologies have shown promise in improving medication awareness. These interventions not only empower patients but also support healthcare providers in delivering personalized care. By fostering a culture of medication literacy, healthcare systems can enhance patient outcomes and reduce the burden of medication-related issues.
Topics for submission:
Assessing medication literacy in diverse populations
Barriers and facilitators to understanding medication indications
Impact of patient education and other related interventions on medication adherence
Tools, interventions and strategies for enhancing patient medication knowledge
Understand how, why for whom and under what circumstances interventions to enhance medication knowledge work or not
This Collection supports and amplifies research related to SDG 3 (Good Health and Well-being).
All manuscripts submitted to this journal, including those submitted to collections and special issues, are assessed in line with our editorial policies and the journal’s peer review process. Reviewers and editors are required to declare competing interests and can be excluded from the peer review process if a competing interest exists.
Publishing Model: Open Access
Deadline: Sep 30, 2026
Promise, perception, and practice: workforce capability and technology integration in healthcare
BMC Health Services Research invites submissions on how health workforce professionals interact with, adopt, and shape the implementation of digital health technologies, artificial intelligence (AI), and modern electronic health record (EHR) systems. Whether these technologies deliver value depends not only on the technical specifications but also on how they are implemented, governed, evaluated, and continuously refined within the organizations and workforces in which they operate. Health systems worldwide are committing to technology portfolios at a pace that consistently outstrips the evidence base needed to guide them, leaving technology program leaders without the knowledge they need to make sound investment and deployment decisions. We particularly welcome work that bridges implementation science, clinical informatics, and health services research to generate evidence actionable for health systems managing growing technology portfolios.
Topics of interest include, but are not limited to:
- Adoption and sustained use: digital literacy, training, and effective human–AI collaboration
- Front-line feedback as a signal for monitoring and improving technology performance
- Case studies of AI tools (clinical systems, ambient documentation, EHRs, decision support) with focus on long-term value and sustainment
- Governance, evaluation frameworks, and learning health system models for continuous assessment
- Impacts on care quality, clinician well-being, efficiency, and costs, including unintended effects (e.g., workflow disruption, alert fatigue)
- Ethical, equity, and policy considerations, including evolving AI governance
- Innovative measurement using EHR logs, administrative data, and observational methods
- Development of standardized evaluation frameworks applicable across technologies and settings
We welcome submissions across all article types accepted by BMC Health Services Research, including research articles, systematic reviews, study protocols, database and software articles.
All manuscripts submitted to this journal, including those submitted to collections and special issues, are assessed in line with our editorial policies and the journal’s peer review process. Reviewers and editors are required to declare competing interests and can be excluded from the peer review process if a competing interest exists.
Publishing Model: Open Access
Deadline: Jan 29, 2027