Blood pressure control with active ultrafiltration measures and without antihypertensives is essential for survival in hemodiafiltration and hemodialysis programs for patients with CKD. A prospective observational study.
Published in Social Sciences, General & Internal Medicine, and Pharmacy & Pharmacology
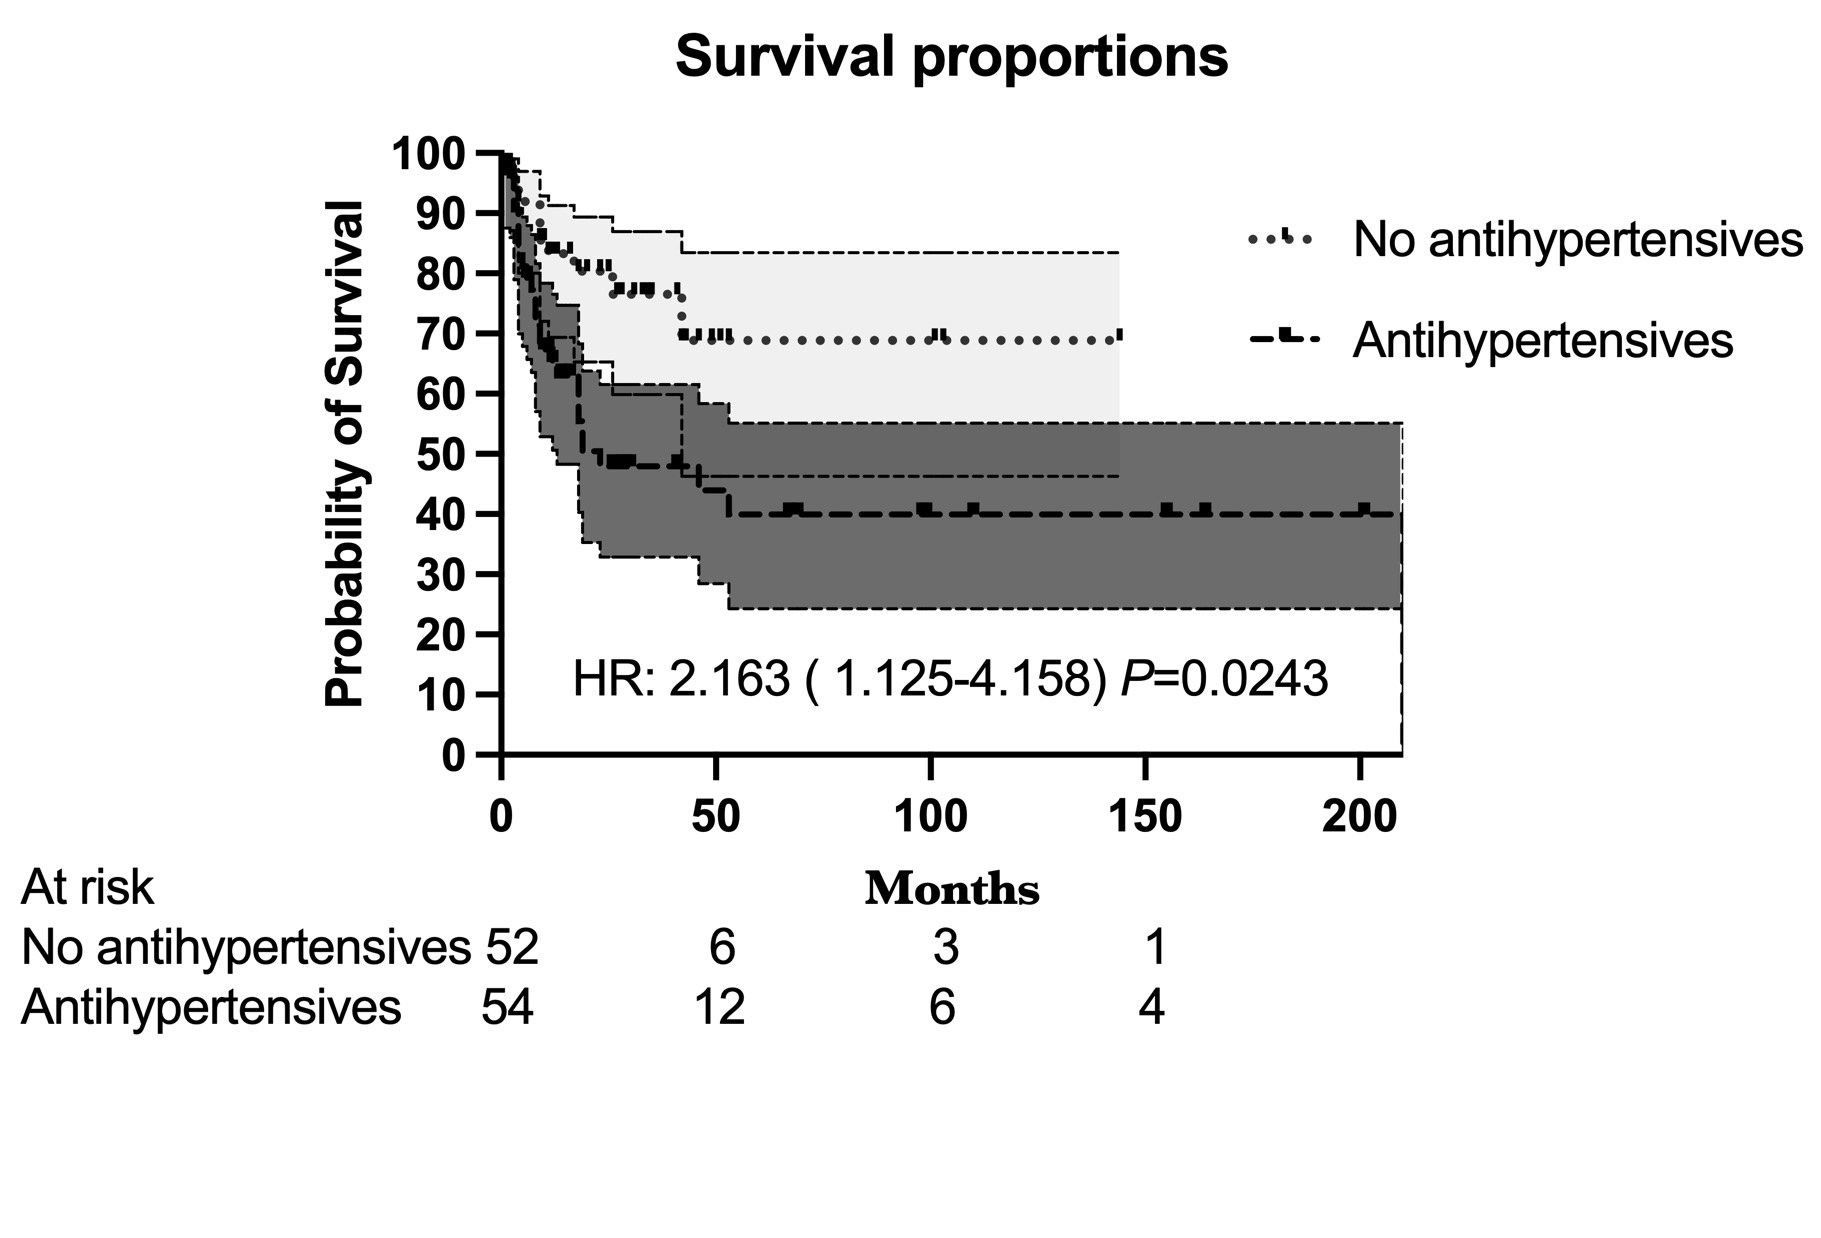
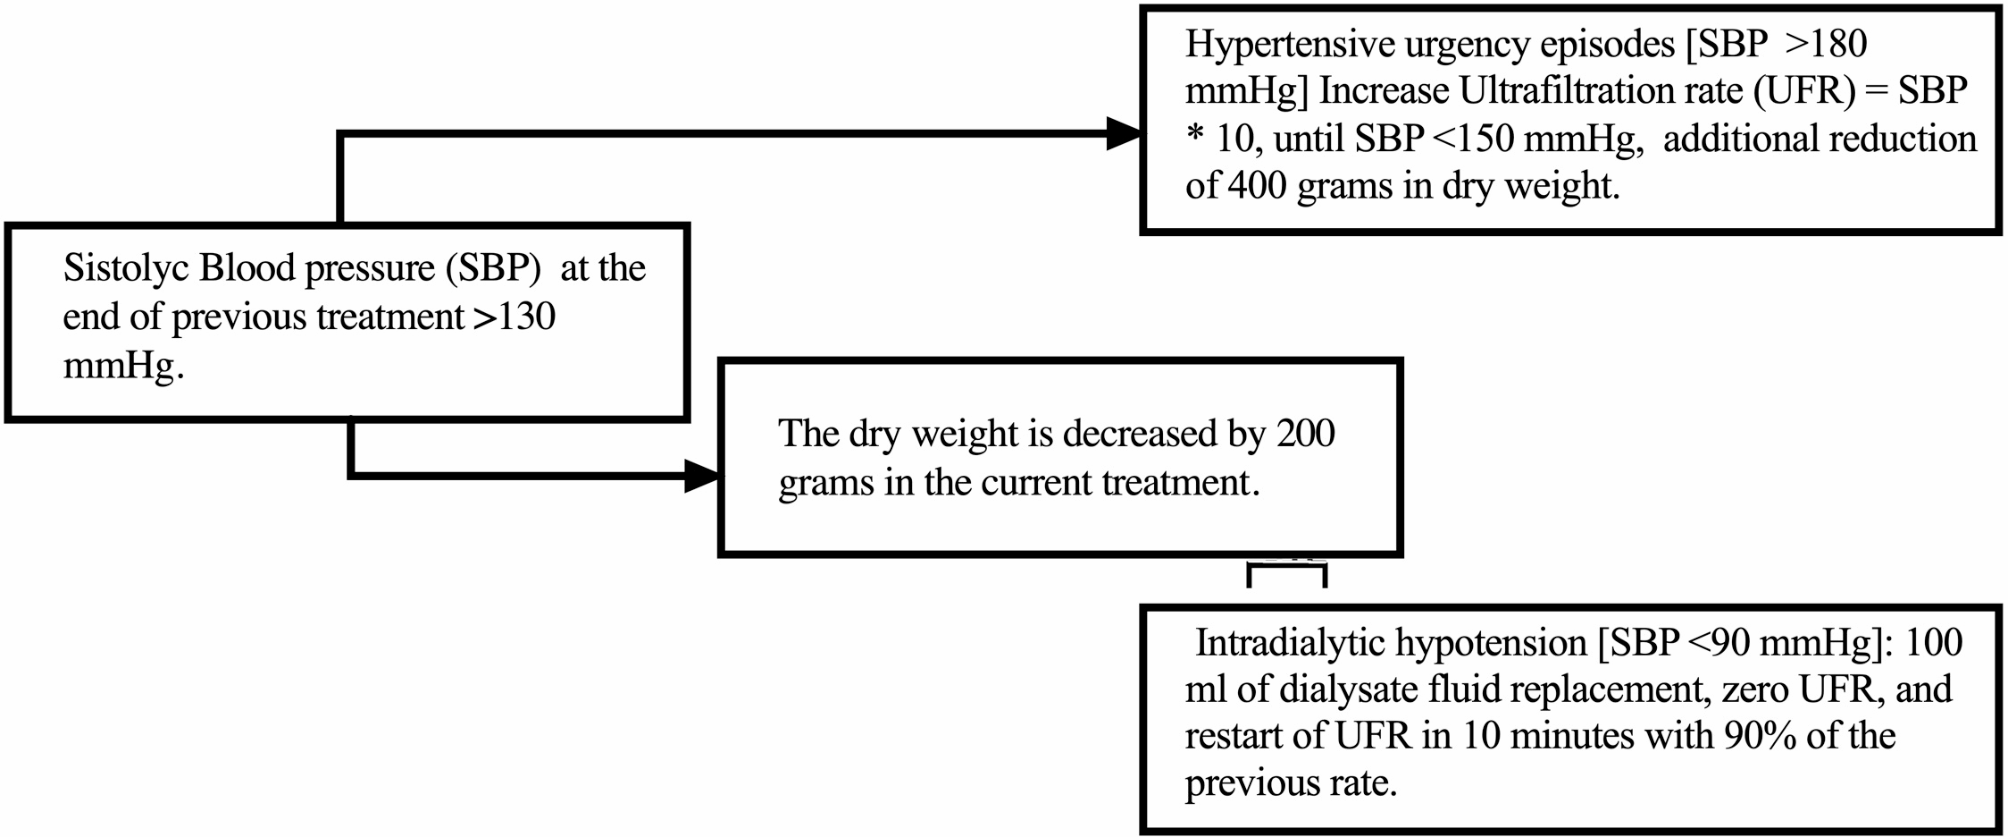

The main finding confirms the hypothesis of the study that there is more remarkable survival in the group of patients with CKD whose hypertension can be controlled without antihypertensive treatment and with the use of constant dry weight reduction measures to optimize ultrafiltration. The factors associated with the lack of control of arterial hypertension were a history of vascular amputation, a history of being an ex-smoker, being a carrier of type 2 diabetes mellitus, having a serum ferritin level greater than 26.75%, being male, and being treated with hemodialysis. The associated protective factors were having a diagnosis of glomerulonephritis as an etiology of chronic kidney disease, a history of never smoking, a serum ALB concentration greater than 4.214 g/dl, effective blood flow greater than 423.5 ml/min, and interdialytic weight gain >4.925%, hemodiafiltration as treatment, urea levels less than 103.78 mg/dl, and fasting glucose levels less than 109.2 mg/dl. According to the time-adjusted model, only four factors were associated: age, transferrin saturation, serum albumin levels, and history of vascular amputation.
In the stratified analysis, differences in survival were demonstrated by the percentiles of blood pressure taken in the last month of survival or censoring. With blood pressures ranging from 141 mmHg to 122 mmHg, there is a proportional risk of death associated with the intake of antihypertensive agents. The same occurs when the blood pressure is less than 105 mmHg. These relationships could not be established with pressures greater than 141 mmHg.

Follow the Topic
-
BMC Nephrology
This is an open access journal publishing original peer-reviewed research articles in all aspects of the prevention, diagnosis and management of kidney and associated disorders, as well as related molecular genetics, pathophysiology, and epidemiology.

Related Collections
With Collections, you can get published faster and increase your visibility.
Equity in kidney care access
In recent years, the field of nephrology has increasingly recognized the critical need for equitable access to kidney care. Healthcare disparities in nephrology represent significant unmet needs for diverse populations. Many patients face socioeconomic barriers that severely limit their access to essential services such as dialysis and transplant resources. Studies have demonstrated that individuals from lower socioeconomic backgrounds are less likely to receive timely referrals for nephrology services and experience poorer health outcomes. These disparities not only complicate clinical management but also exacerbate the overall public health burden associated with chronic kidney disease (CKD).
Researchers have begun exploring the impact of community-based approaches to kidney care, highlighting the importance of tailored patient education and culturally sensitive healthcare practices. Additionally, policy frameworks that promote inclusivity in kidney care have emerged, demonstrating a commitment to reducing barriers and ensuring that all individuals have access to necessary resources.
Advancements in telemedicine and mobile health technologies present new avenues for expanding access to nephrology services, particularly in underserved areas. Furthermore, investigating the role of social determinants of health will provide critical insights that can inform holistic strategies to improve kidney care equity.
Important topics of interest include but are not limited to:
- Socioeconomic barriers to dialysis
- Equitable distribution of transplant resources
- Policy frameworks for kidney care inclusivity
- Global access gaps in renal treatment
- Innovative community-based interventions
- Telemedicine in nephrology
- Social determinants of kidney health
This Collection supports and amplifies research related to SDG 3: Good Health and Well-being.
All manuscripts submitted to this journal, including those submitted to collections and special issues, are assessed in line with our editorial policies and the journal’s peer review process. Reviewers and editors are required to declare competing interests and can be excluded from the peer review process if a competing interest exists.
Publishing Model: Open Access
Deadline: Mar 26, 2027
Mental health integration in nephrology
The intersection of mental health and nephrology is gaining increasing recognition as a critical component of integrated patient care. Chronic kidney disease (CKD), along with treatments such as dialysis and kidney transplantation, is frequently associated with significant psychological distress, leading to poorer health outcomes. This Collection aims to explore the integration of mental health support within nephrology practices, addressing how psychological factors influence disease management and patient quality of life.
Recent advances in this field include the implementation of routine depression screening in dialysis settings and the development of integrated behavioral health models within nephrology clinics. These strategies have shown promise in addressing the psychological needs of patients and their family caregivers, fostering better adherence to treatment regimens, and ultimately improving physical and mental well-being among this population.
We welcome submissions including original research, reviews, and implementation studies. Topics of interest include, but are not limited to:
- Psychological support in CKD
- Depression screening in dialysis and transplant patients
- Integrated behavioral health in nephrology care
- Cognitive and behavioral interventions in CKD management
- Digital mental health interventions in nephrology
- Dyadic and family-based interventions in CKD management
This Collection supports and amplifies research related to SDG 3: Good Health and Well-being
All manuscripts submitted to this journal, including those submitted to collections and special issues, are assessed in line with our editorial policies and the journal’s peer review process. Reviewers and editors are required to declare competing interests and can be excluded from the peer review process if a competing interest exists.
Publishing Model: Open Access
Deadline: Jan 30, 2027