Geographical variation and associated factors of childhood measles vaccination in Ethiopia: a spatial and multilevel analysis
Published in Biomedical Research, Immunology, and Public Health


Background
In Ethiopia, despite considerable improvement of measles vaccination, measles outbreaks is occurring in most parts of the country. Understanding the neighborhood variation in childhood measles vaccination is crucial for evidence-based decision-making. However, the spatial pattern of measles-containing vaccine (MCV1) and its predictors are poorly understood. Hence, this study aimed to explore the spatial pattern and associated factors of childhood MCV1 coverage.
Methods
An in-depth analysis of the 2016 Ethiopia demographic and health survey data was conducted, and a total of 3722 children nested in 611 enumeration areas were included in the analysis. Global Moran’s I statistic and Poisson-based purely spatial scan statistics were employed to explore spatial patterns and detect spatial clusters of childhood MCV1, respectively. Multilevel logistic regression models were fitted to identify factors associated with
childhood MCV1.
Results
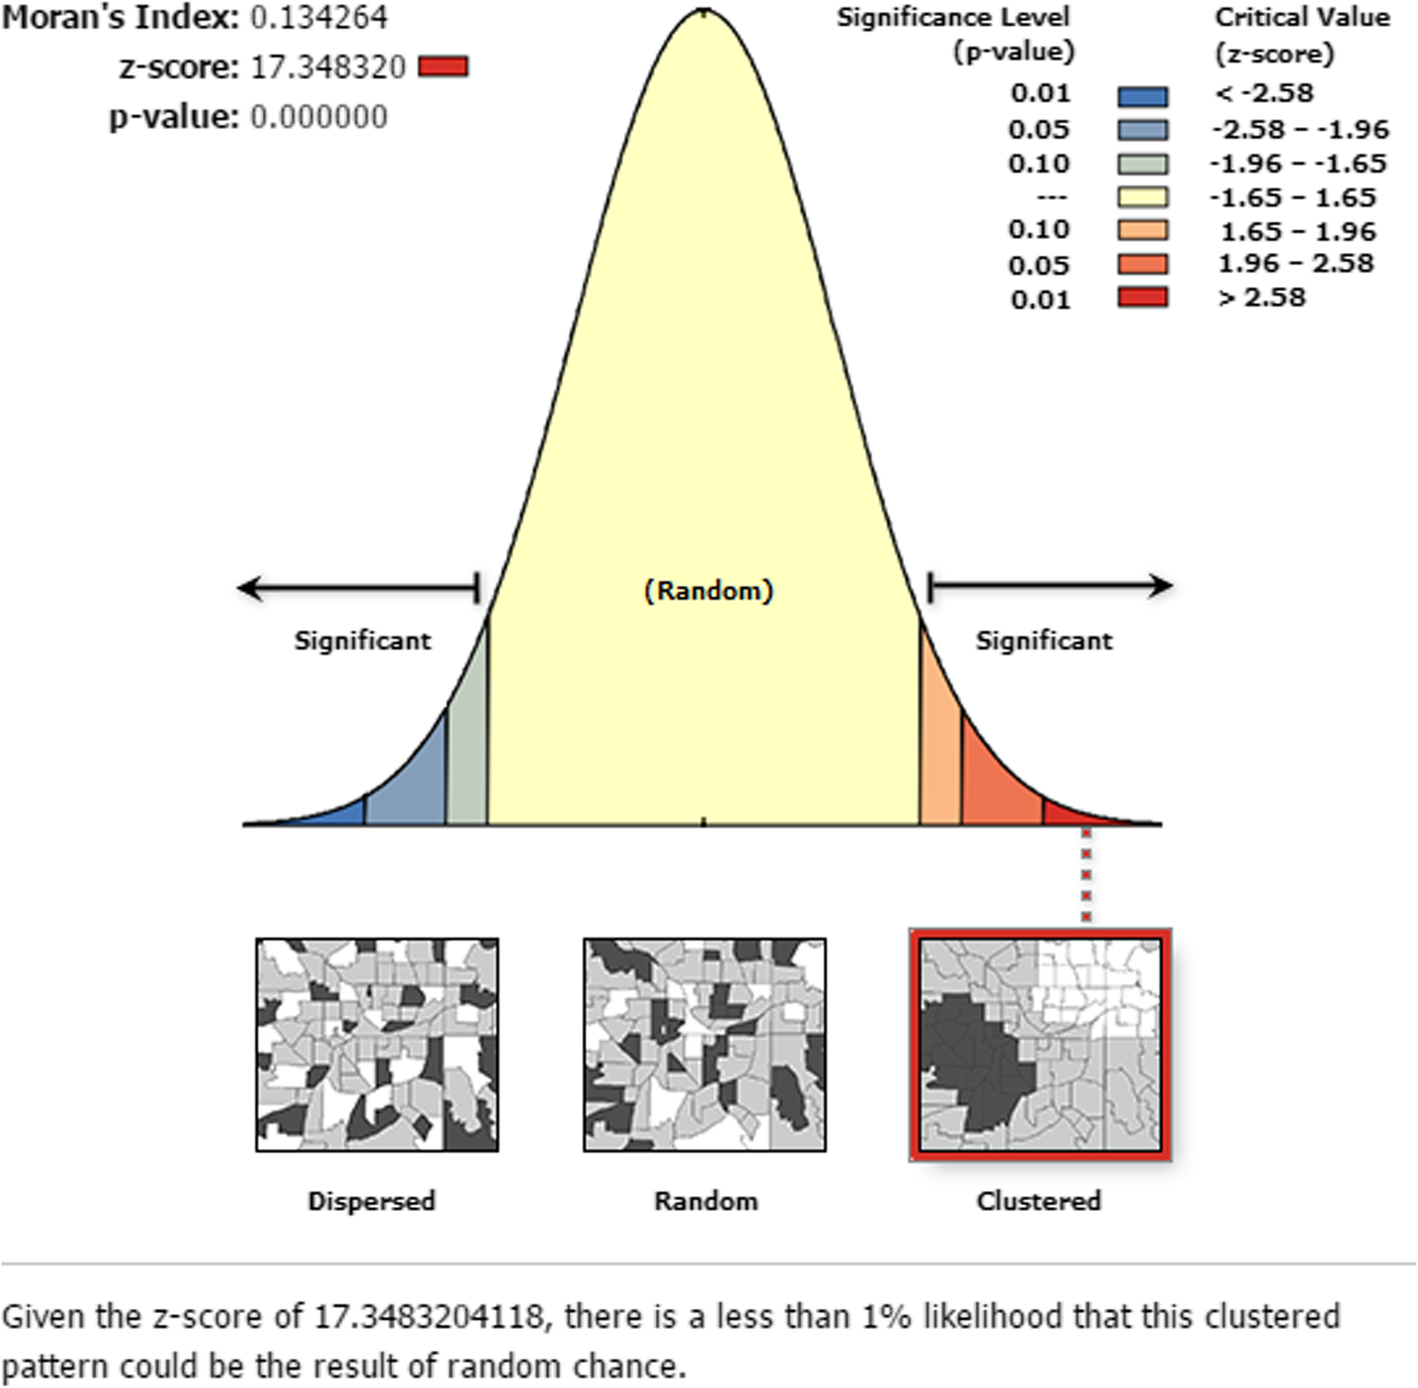
Spatial heterogeneity of childhood MCV1 was observed (Global Moran’s I = 0.13, p-value < 0.0001), and seven significant SaTScan clusters of areas with low MCV1 coverage were detected. The most likely primary SaTScan cluster was detected in the Afar Region, secondary cluster in Somali Region, and tertiary cluster in Gambella Region. In the final model of the multilevel analysis, individual and community level factors accounted for 82% of the variance in the odds of MCV1 vaccination. Child age (AOR = 1.53; 95%CI: 1.25–1.88), pentavalent vaccination first dose (AOR = 9.09; 95%CI: 6.86–12.03) and third dose (AOR = 7.12; 95%CI: 5.51–9.18, secondary and above maternal education (AOR = 1.62; 95%CI: 1.03–2.55) and media exposure were the factors that increased the odds of MCV1 vaccination at the individual level. Children with older maternal age had lower odds of receiving MCV1. Living in
Afar, Oromia, Somali, Gambella and Harari regions were factors associated with lower odds of MCV1 from the community-level factors. Children far from health facilities had higher odds of receiving MCV1 (AOR = 1.31, 95%CI =1.12–1.61).
Conclusion
A clustered pattern of areas with low childhood MCV1 coverage was observed in Ethiopia. Both individual and community level factors were significant predictors of childhood MCV1. Hence, it is good to give priority for the areas with low childhood MCV1 coverage, and to consider the identified factors for vaccination interventions.
Keywords
Measles, Vaccination, Spatial, Multilevel, Ethiopia

Tesfahun Taddege GEREMEW is a senior public health specialist and Global health security (GHS) advisor with extensive experience in public health emergency management (PHEM), public health research, health information system and data analytics. He holds two master’s degrees in public health - MPH in Field Epidemiology (Ethiopian FELTP) and MPH in Reproductive Health-along with a bachelor’s degree (BSc) in public health.
Currenly, he's warking for The Ohio State University, Global One Health Initietive (GOHi) as a Global Health Security (GHS) Advisor seconded to Amhara Public Health Institute (APHI)
He is passionate about how strong public health security and quality data may make our world safer.
Follow the Topic
-
BMC Public Health
An open access, peer-reviewed journal that considers articles on the epidemiology of disease and the understanding of all aspects of public health.

Related Collections
With Collections, you can get published faster and increase your visibility.
Appropriate use of antibiotics: public health strategies, knowledge, and practice gaps
BMC Public Health is calling for submissions to our Collection on Appropriate use of antibiotics: public health strategies, knowledge, and practice gaps.
Misuse of antibiotics contributes to antimicrobial resistance (AMR), posing a threat to the future management of bacterial diseases. However, it is a multi-faceted problem without a simple solution.
Antibiotic misuse can take various forms, each requiring different strategies to address. In healthcare systems, antibiotic overuse is often driven by the tension between clinical uncertainty and the desire to offer patients a treatment that may improve their symptoms or prevent them from developing complications. The prescription of antibiotics is often done empirically, driven by the difficulty of distinguishing between bacterial and viral infections at the point of care, or the worry that a lack of intervention could have consequences.
Added to this, people in the community can contribute to inappropriate use by reusing or sharing leftover antibiotics from prior prescriptions. Similarly, misplaced expectations around the benefits of antibiotics can drive misuse in the community, pointing to the need for community-focused and community-led initiatives to inform the public on the use of antibiotics and the collective impact of antimicrobial resistance.
However, social science reframes antibiotic overuse as more than an individual behaviour problem. Antibiotics frequently act as a social and structural “quick fix” that supports care, productivity, hygiene, and coping with inequality in everyday life. They are used to compensate for gaps in water, sanitation, social protection, and health-system capacity, suggesting that interventions focusing narrowly on individual knowledge and attitudes may be unlikely to succeed unless they also address these wider drivers.
This Collection aims to explore the various dimensions of the responsible use of antibiotics, examining the prevalence of misuse and strategies for reducing unnecessary use, covering interventions aimed at prescribers and pharmacists as well as 'bottom-up' strategies such as community education campaigns. We invite contributions that investigate the roles of healthcare providers, patients, professional guidance, communities, and policymakers in addressing this pressing issue.
Potential topics for submission include, but are not limited to:
Patterns of antibiotics overuse in various populations
The role of healthcare providers in preventing misuse
Public health campaigns and gross-roots initiatives to promote responsible use of antibiotics
Policy frameworks for improving the prescribing and dispensing of antibiotics
Social and structural drivers of antibiotic use (ethnographic, anthropological, and political-economy analyses).
Interventions that address upstream determinants (water, sanitation, social protection, labour conditions) alongside stewardship measures.
This Collection supports and amplifies research related to SDG 3 (Good Health and Well-being).
All manuscripts submitted to this journal, including those submitted to collections and special issues, are assessed in line with our editorial policies and the journal’s peer review process. Reviewers and editors are required to declare competing interests and can be excluded from the peer review process if a competing interest exists.
Publishing Model: Open Access
Deadline: Oct 03, 2026
Digital exclusion and health equity
Digital exclusion poses significant barriers to health equity, particularly in the context of an increasingly technology-driven healthcare landscape. Many individuals, especially from underserved communities face challenges in accessing digital health resources, including telehealth services, electronic health records, and health information online, alongside challenges from other social determinants of health. This Collection seeks to explore the intersection of digital health access and health equity, focusing on the disparities that arise from unequal access to digital tools and resources.
Addressing digital health exclusion is critical for promoting health equity and ensuring that all individuals can benefit from advancements in digital health. Recent strides in telehealth and digital health interventions have demonstrated the potential for technology to improve access to care, yet they also reveal significant disparities that must be acknowledged. By understanding the factors that contribute to eHealth disparities, we can develop targeted digital inclusion strategies that address the unique needs of diverse populations, ultimately fostering a more equitable health system.
Topics for submission include but are not limited to:
- Equitable digital health systems: policy, infrastructure, and community engagement
- Digital health access among underserved communities
- Digital literacy and health outcomes across diverse populations
- Innovations and implementation strategies for bridging digital health gaps in underserved communities
- Measuring and monitoring digital health disparities: metrics and methodologies
This Collection supports and amplifies research related to SDG 3 (Good Health and Well Being) and SDG 10: (Reduced Inequalities).
All manuscripts submitted to this journal, including those submitted to collections and special issues, are assessed in line with our editorial policies and the journal’s peer-review process. Reviewers and editors are required to declare competing interests and can be excluded from the peer review process if a competing interest exists.
Publishing Model: Open Access
Deadline: Dec 11, 2026