Why promising cancer treatments fall short: connecting resistance biology, clinical trials, and withdrawn therapies
Published in Bioengineering & Biotechnology, Cancer, and General & Internal Medicine

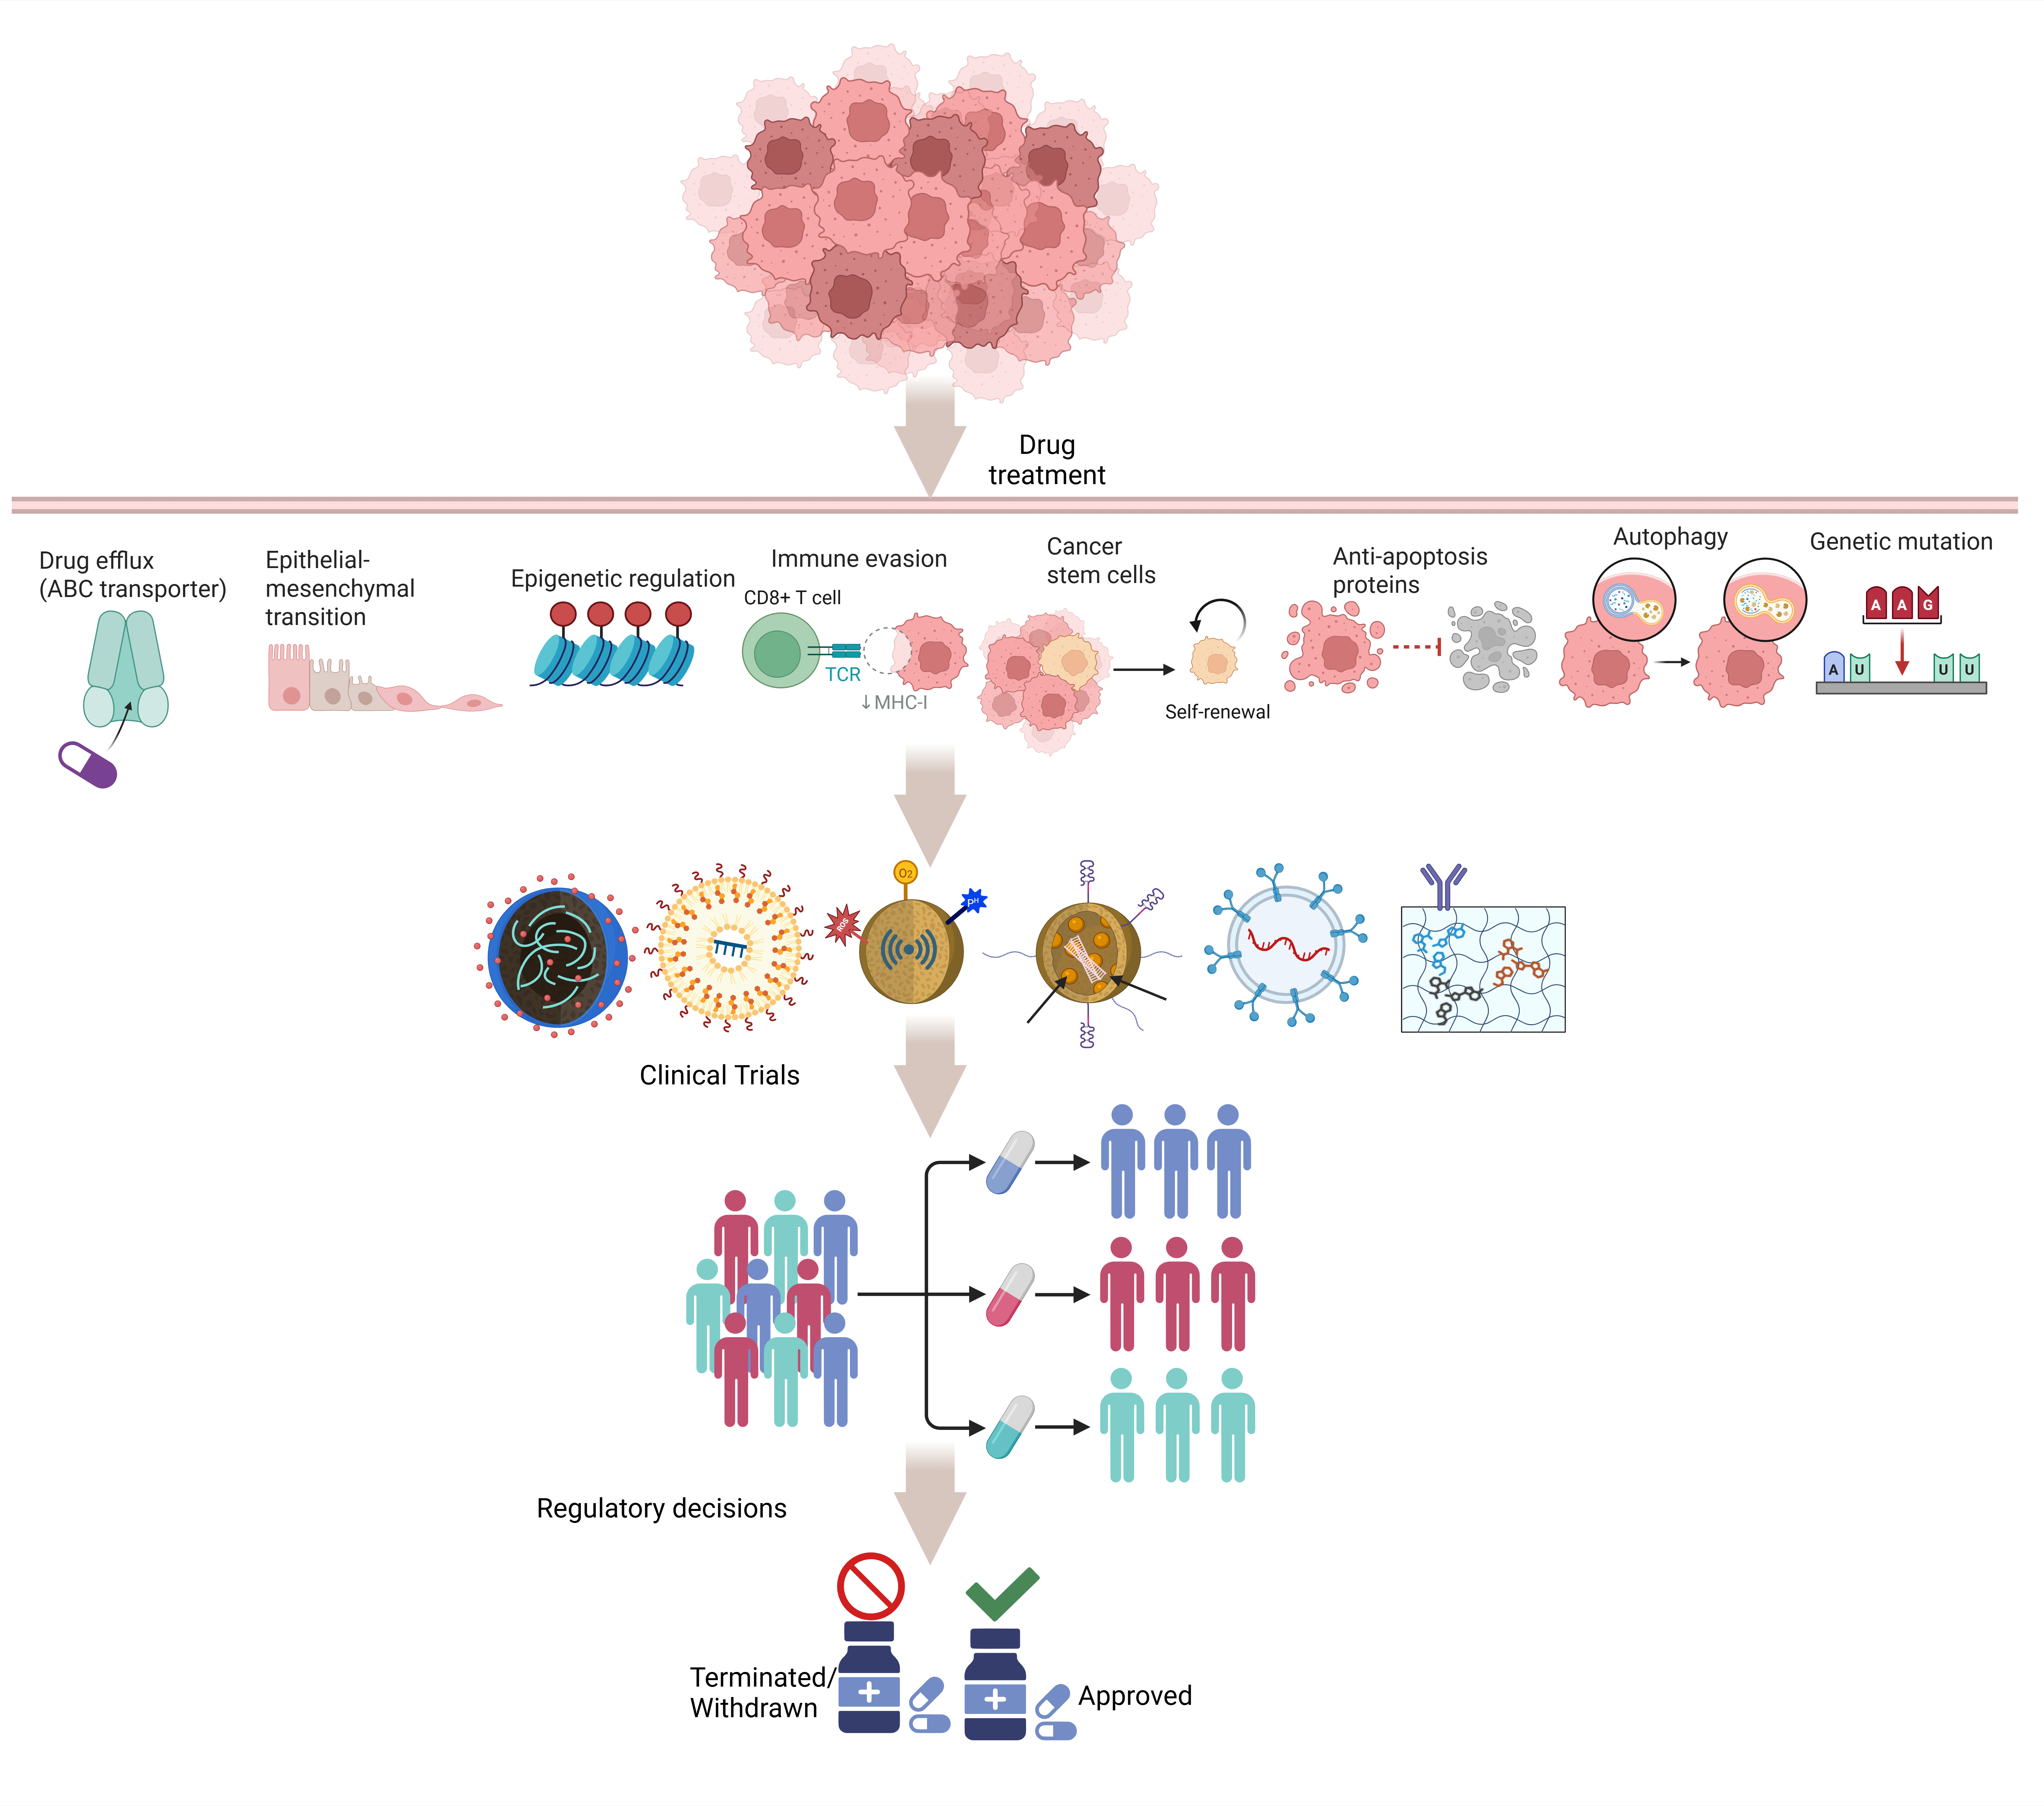

Why do promising cancer treatments sometimes fail to deliver lasting benefits?
A compelling biological target, an effective delivery system, and encouraging early results are important steps. Yet understanding a treatment’s potential also requires examining what happens when it reaches clinical testing and what can be learned when development stops or an approval is withdrawn.
Our review, published in the Journal of Experimental & Clinical Cancer Research, brings these questions together. We connect the biology of chemotherapy resistance with the clinical experience of developing treatments, examining both therapeutic opportunities and the obstacles encountered along the way.
Connecting the tumor environment with resistance
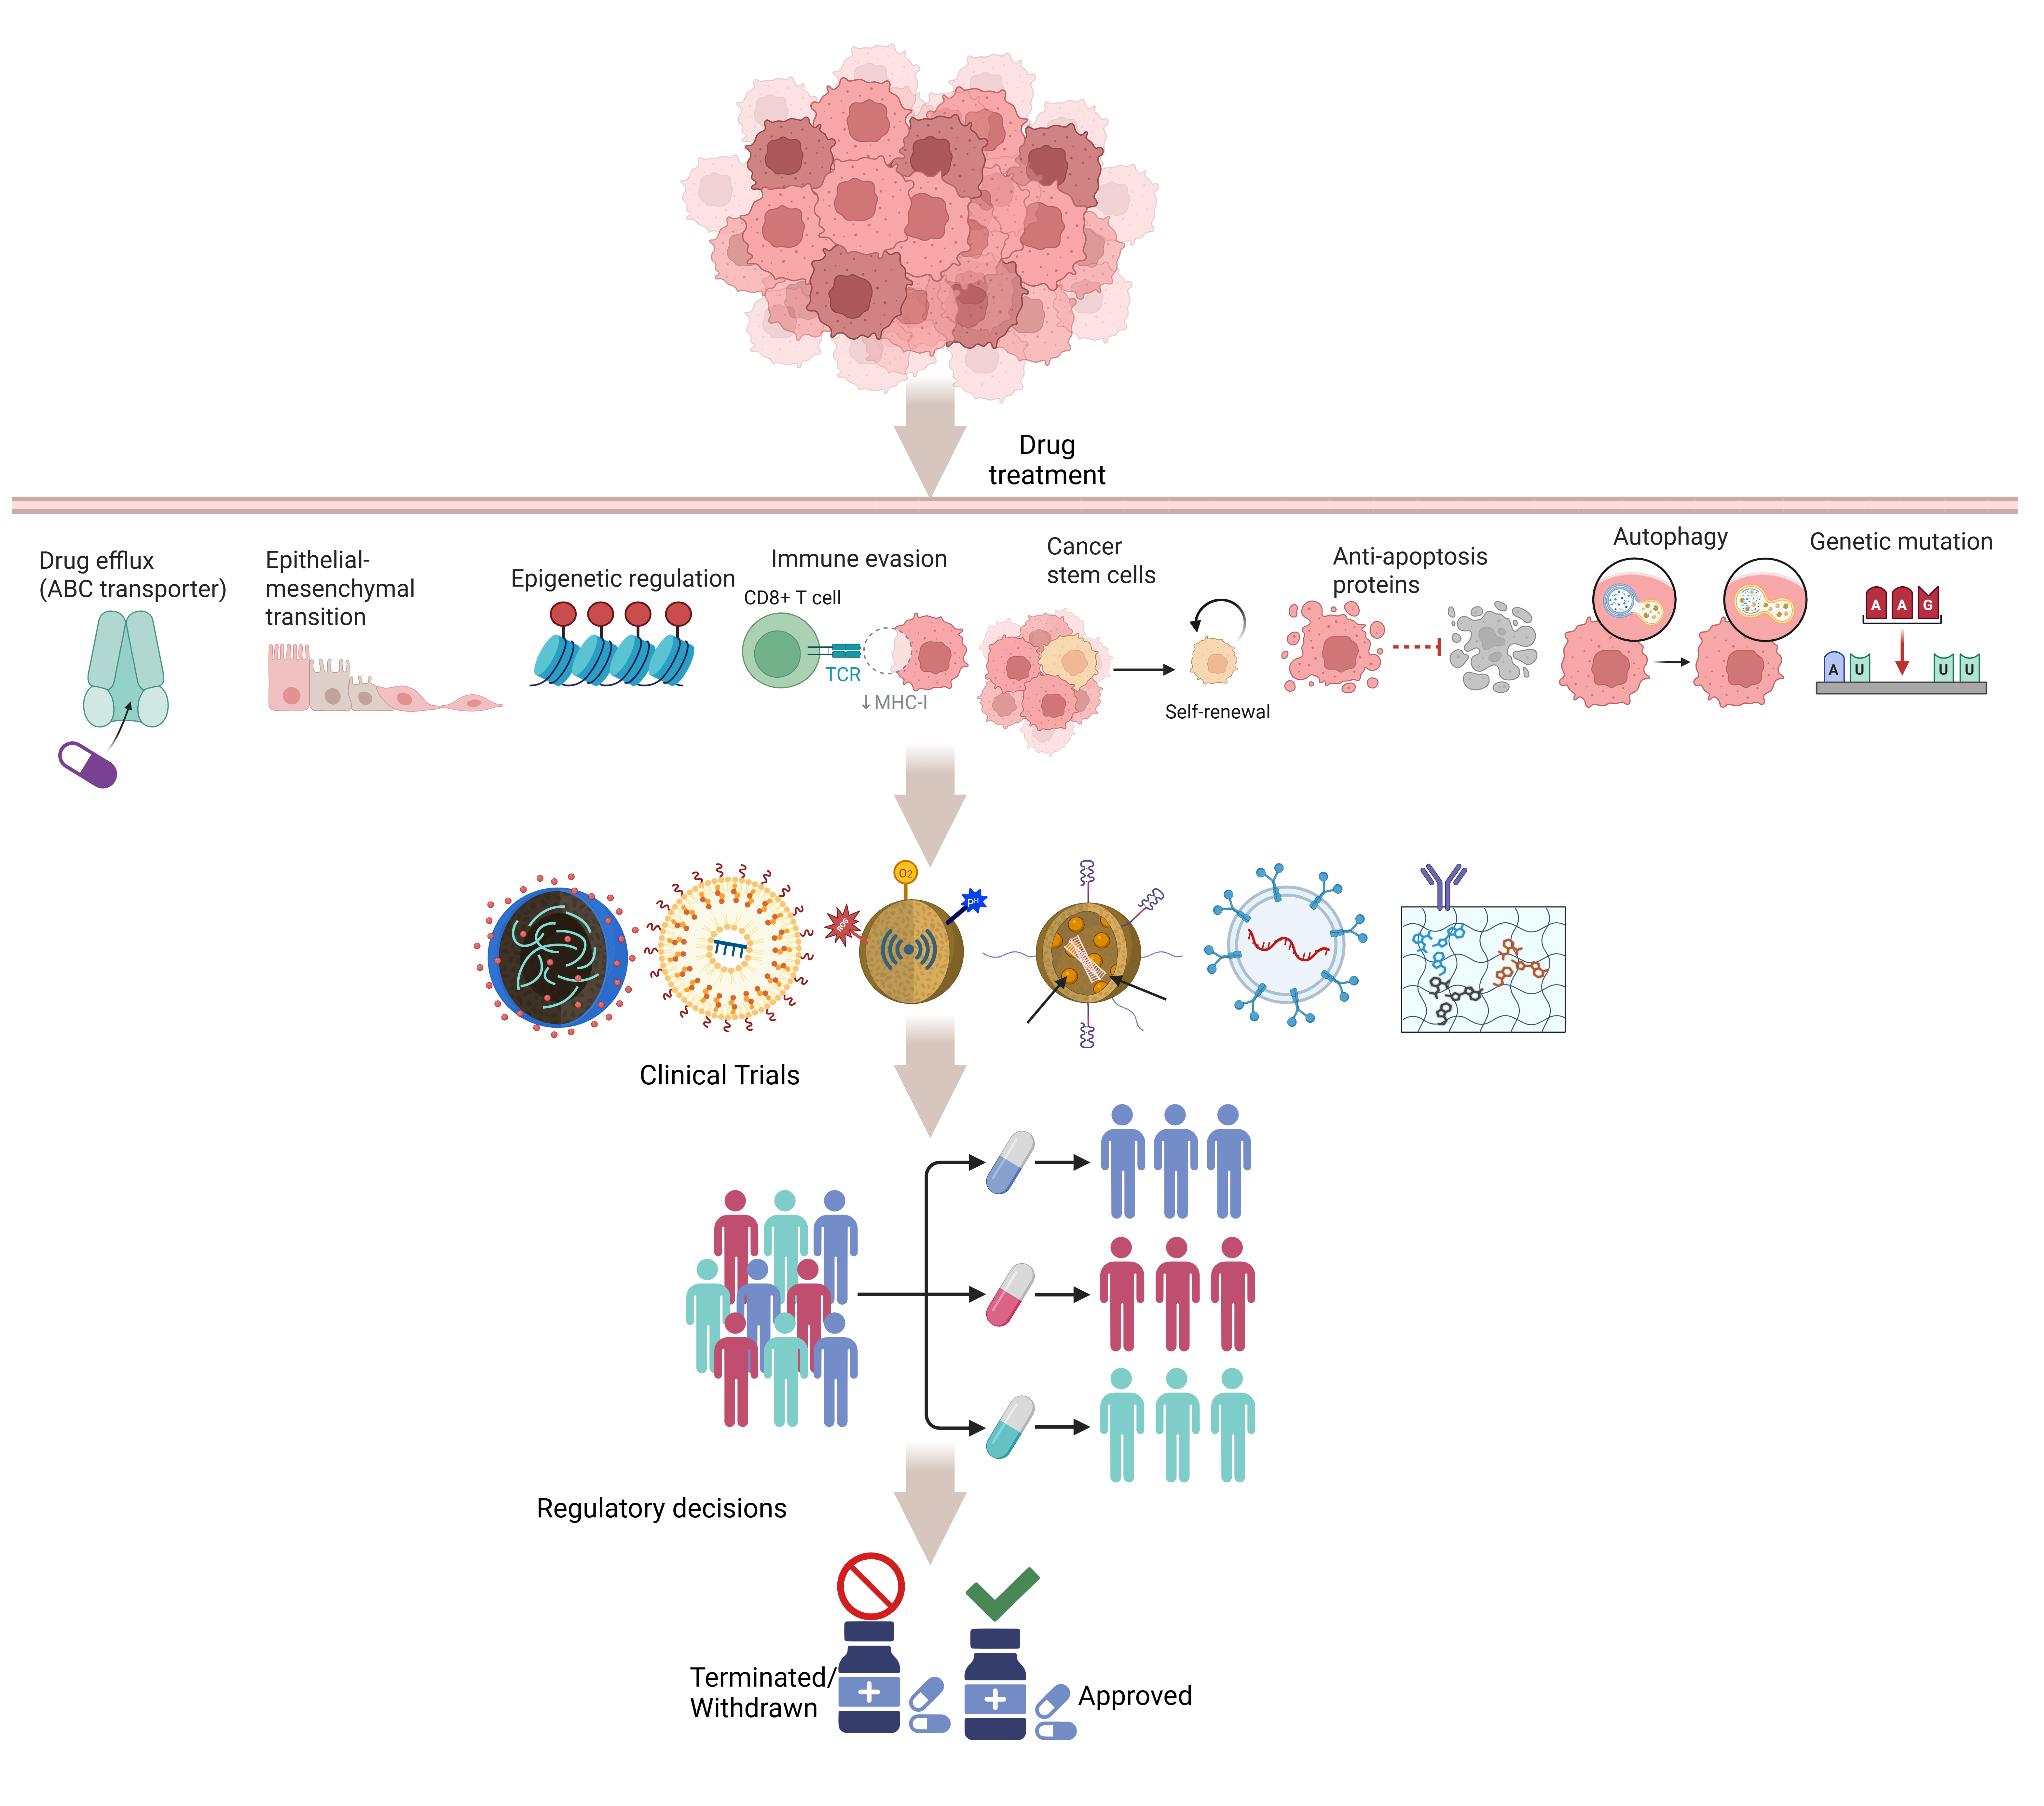
Cancer cells exist within a surrounding network of stromal cells, immune cells, blood vessels, and extracellular matrix. Low oxygen, acidity, and signals from neighboring cells can influence how cancer cells survive treatment.
Our review examines how these conditions interact with cellular signaling and epigenetic regulation, changes in gene activity that do not require changes to the DNA sequence. DNA methylation, histone modifications, and microRNA networks can help maintain resistant cellular states. These processes interact, making it important to consider how an intervention affects the wider system.
This work provides the biological foundation for the therapeutic strategies discussed throughout the article.
Where nanotechnology and gene therapy could intervene
Nanotechnology offers ways to deliver therapeutic cargo and combine agents within a delivery platform. Gene-based approaches offer tools for modifying the molecular processes that sustain resistance.
We examine these approaches alongside epigenetic treatments and combination strategies. The central question is how to match an intervention to a defined resistance mechanism while ensuring that it reaches the appropriate cells.
That requires addressing practical limitations: uneven nanoparticle accumulation, poor penetration through tumor tissue, immune clearance, gene-delivery efficiency, and potential off-target effects. A promising mechanism must be accompanied by evidence that the intended intervention can work under clinically relevant conditions.
What do clinical trials contribute to this understanding?
An important part of our review is its examination of clinical-trial experience across nanomedicine, gene-targeting approaches, and combination immunotherapies.
The trial summaries allow readers to consider therapeutic concepts alongside their development stage and reported outcomes. We also examine terminated or withdrawn studies and the reasons reported for stopping them, including safety concerns, insufficient efficacy, recruitment difficulties, funding interruptions, and changes in development priorities.
These distinctions matter. A completed trial does not automatically establish clinical benefit, and a terminated trial does not necessarily demonstrate that the underlying biological strategy was ineffective. Interpreting the reason for an outcome is essential to deciding what should change in the next study.
Learning from withdrawn oncology treatments
The review also examines withdrawn oncology drugs or indications and the importance of confirming benefit after initial approval.
Drug withdrawals, indication-specific withdrawals, and discontinued investigational programs represent different situations. Considering them separately helps avoid treating every setback as the same kind of failure.
For researchers, these examples raise important questions about the evidence needed to advance a treatment. Which endpoints establish meaningful benefit? How should early signals be tested? What information is needed to identify the patients most likely to respond?
These questions make clinical and regulatory experience directly relevant to experimental design.
Making resistance biology visible in treatment failure
Our review highlights a communication gap between the biological understanding of cancer resistance and how treatment failures are described. Labels such as “lack of efficacy” or “failure to confirm clinical benefit” document an outcome but can leave the underlying resistance mechanisms unexplained even where relevant molecular evidence exists.
We argue that this gap matters beyond terminology. How failures are explained can influence research priorities, funding decisions, and the design of subsequent therapies. When evidence of tumor adaptation receives insufficient attention, opportunities to develop resistance-focused treatments and predictive biomarkers may be missed.
The review calls for closer integration of molecular resistance data with clinical outcomes and regulatory summaries, greater transparency around emerging resistance mechanisms, and trial designs that account for tumor evolution.
Learning from discontinued trials and withdrawn treatments should help us identify what future therapies must address to achieve durable benefit.
Looking ahead
For me, the value of this review lies in bringing mechanistic detail, therapeutic design, clinical experience, and development setbacks into one discussion.
The resulting priorities include better biomarkers for patient selection, more representative experimental models, improved delivery, and carefully justified treatment combinations. These priorities can help researchers formulate studies that test both whether an intervention works and whether it works for the intended reason.
I am grateful to all my co-authors for their contributions. I hope the review is useful to researchers designing new platforms, clinicians following emerging treatments, and readers seeking a connected view of chemoresistance.
What should future trials measure to explain treatment failure more clearly—and help the next generation of therapies avoid repeating it?
Read the full review:
Transforming tumor microenvironments: nanotechnology and gene therapy in cellular signaling and epigenetic insight into chemoresistance
https://doi.org/10.1186/s13046-026-03720-8
Follow the Topic
-
Journal of Experimental & Clinical Cancer Research
Journal of Experimental & Clinical Cancer Research is an online peer-reviewed journal that publishes original research papers, reviews and commentaries in cancer research, from bench to bedside.

Related Collections
With Collections, you can get published faster and increase your visibility.
Insights into the relationship between metabolism and cancer
Cancer metabolism has become one of the most studied aspects of the "hallmarks of cancer." It refers to alterations in how tumor cells process nutrients to fuel their rapid proliferation and spread. These dramatic dysregulations include elevated glucose uptake even in the presence of oxygen (the Warburg effect), dependence on glutamine, and the production of waste products such as lactate, which further support tumor growth and metastasis. Genetic mutations accumulating during cancer progression in metabolic enzymes and cancer-promoting signaling pathways directly affect metabolic changes in cancer cells as well as in the tumor microenvironment [1,2].
A growing number of scientists are developing targeted therapies to exploit these metabolic differences to slow or halt cancer progression. Some therapies aim to block or alter the production of specific metabolites, while several drugs for other pathologies, such as diabetes, are of great interest due to their potential to slow tumor growth by altering systemic metabolic factors such as insulin and glucose levels in a "drug repositioning" strategy [3-7].
Cancer metabolism, involving altered lipid, iron, and amino acid pathways, regulates ferroptosis, an iron-dependent, lipid peroxidation-driven form of cell death. Cancer cells often resist this process, but targeting their specific metabolic vulnerabilities, such as glutathione depletion or iron overload, can trigger ferroptosis to kill tumor cells and overcome drug resistance [8].
Cancer cells can rewire their metabolism when one pathway is blocked, so it is becoming clear that combining metabolism inhibitors with traditional chemotherapy, radiotherapy, or immunotherapy may be an effective therapeutic strategy [8]. While some metabolism-targeting drugs have been successful (e.g., in Acute Lymphocytic Leukemia), targeting cancer metabolism is complex due to its similarity to normal cell processes [9]. Metabolic profiling of patients is helping to identify specific vulnerabilities, leading to more personalized metabolic therapies [10].
Understanding cancer metabolism at a deeper mechanistic level is also essential to improving immunotherapy, as immune cell metabolism changes during therapy administration, contributing to acquired resistance.
KEYWORDS: metabolomics; proteomics, genomics, mitochondrial metabolism, ferroptosis, oxidative stress, inflammation, innovative study models, new translational therapeutic approaches.
In this Collection of the Journal of Experimental & Clinical Cancer Research, we would like to promote studies that further dissect the molecular mechanisms through which cancer cells reprogram their own metabolism and that of cells in the tumor microenvironment, thus driving disease progression. Furthermore, studies that highlight potential metabolic vulnerabilities that could be targeted therapeutically will be of interest.
References
- Finley LWS. What is cancer metabolism? Cell. 2023;186(8):1670-88. PubMed PMID: 36858045. PMCID: PMC10106389.eng
- Guertin DA, Wellen KE. Acetyl-CoA metabolism in cancer. Nat Rev Cancer. 2023;23(3):156. PubMed PMID: 36658431. PMCID: PMC11137663.eng
- Vander Heiden MG. Targeting cancer metabolism: a therapeutic window opens. Nat Rev Drug Discov. 2011;10(9):671-84. PubMed PMID: 21878982.
- Zou W, Han Z, Wang Z, Liu Q. Targeting glutamine metabolism as a potential target for cancer treatment. J Exp Clin Cancer Res. 2025;44(1):180. PubMed PMID: 40598593. PMCID: PMC12210561.
- Formenti L, Abramo F, Dellavedova G, Dematteis V, Decio A, Grasselli C, et al. Impairment of oxidative metabolism compromises Rad51 recruitment and potentiates PARP inhibitor effectiveness in ovarian cancer. J Exp Clin Cancer Res. 2026;45(1):45. PubMed PMID: 41530766. PMCID: PMC12888472.
- Chen T, Xu ZG, Luo J, Manne RK, Wang Z, Hsu CC, et al. NSUN2 is a glucose sensor suppressing cGAS/STING to maintain tumorigenesis and immunotherapy resistance. Cell Metab. 2023;35(10):1782-98.e8. PubMed PMID: 37586363. PMCID: PMC10726430.
- Pillai U J, Ray A, Maan M, Dutta M. Repurposing drugs targeting metabolic diseases for cancer therapeutics. Drug Discov Today. 2023;28(9):103684. PubMed PMID: 37379903.
- Wu Y, Li H, Yue K, Jing C, Duan Y. Ferroptosis in cancer: metabolism, mechanisms and therapeutic prospects. Mol Cancer. 2025;24(1):303.
- Punnasseril JMJ, Auwal A, Gopalan V, Lam AK, Islam F. Metabolic Reprogramming of Cancer Cells and Therapeutics Targeting Cancer Metabolism. Cancer Med. 2025;14(18):e71244. PubMed PMID: 40956032. PMCID: PMC12439291.
- da Silva-Diz V, Herranz D. Unleashing the Full Potential of Metabolic Interventions in T-ALL. Blood Cancer Discov. 2025;6(3):163-7. PubMed PMID: 40111138. PMCID: PMC12050939.
- Benjamin DI, Cravatt BF, Nomura DK. Global profiling strategies for mapping dysregulated metabolic pathways in cancer. Cell Metab. 2012;16(5):565-77. PubMed PMID: 23063552. PMCID: PMC3539740.
Publishing Model: Open Access
Deadline: Feb 28, 2027

