Why promising cancer treatments fall short: connecting resistance biology, clinical trials, and withdrawn therapies
Published in Bioengineering & Biotechnology, Cancer, and General & Internal Medicine
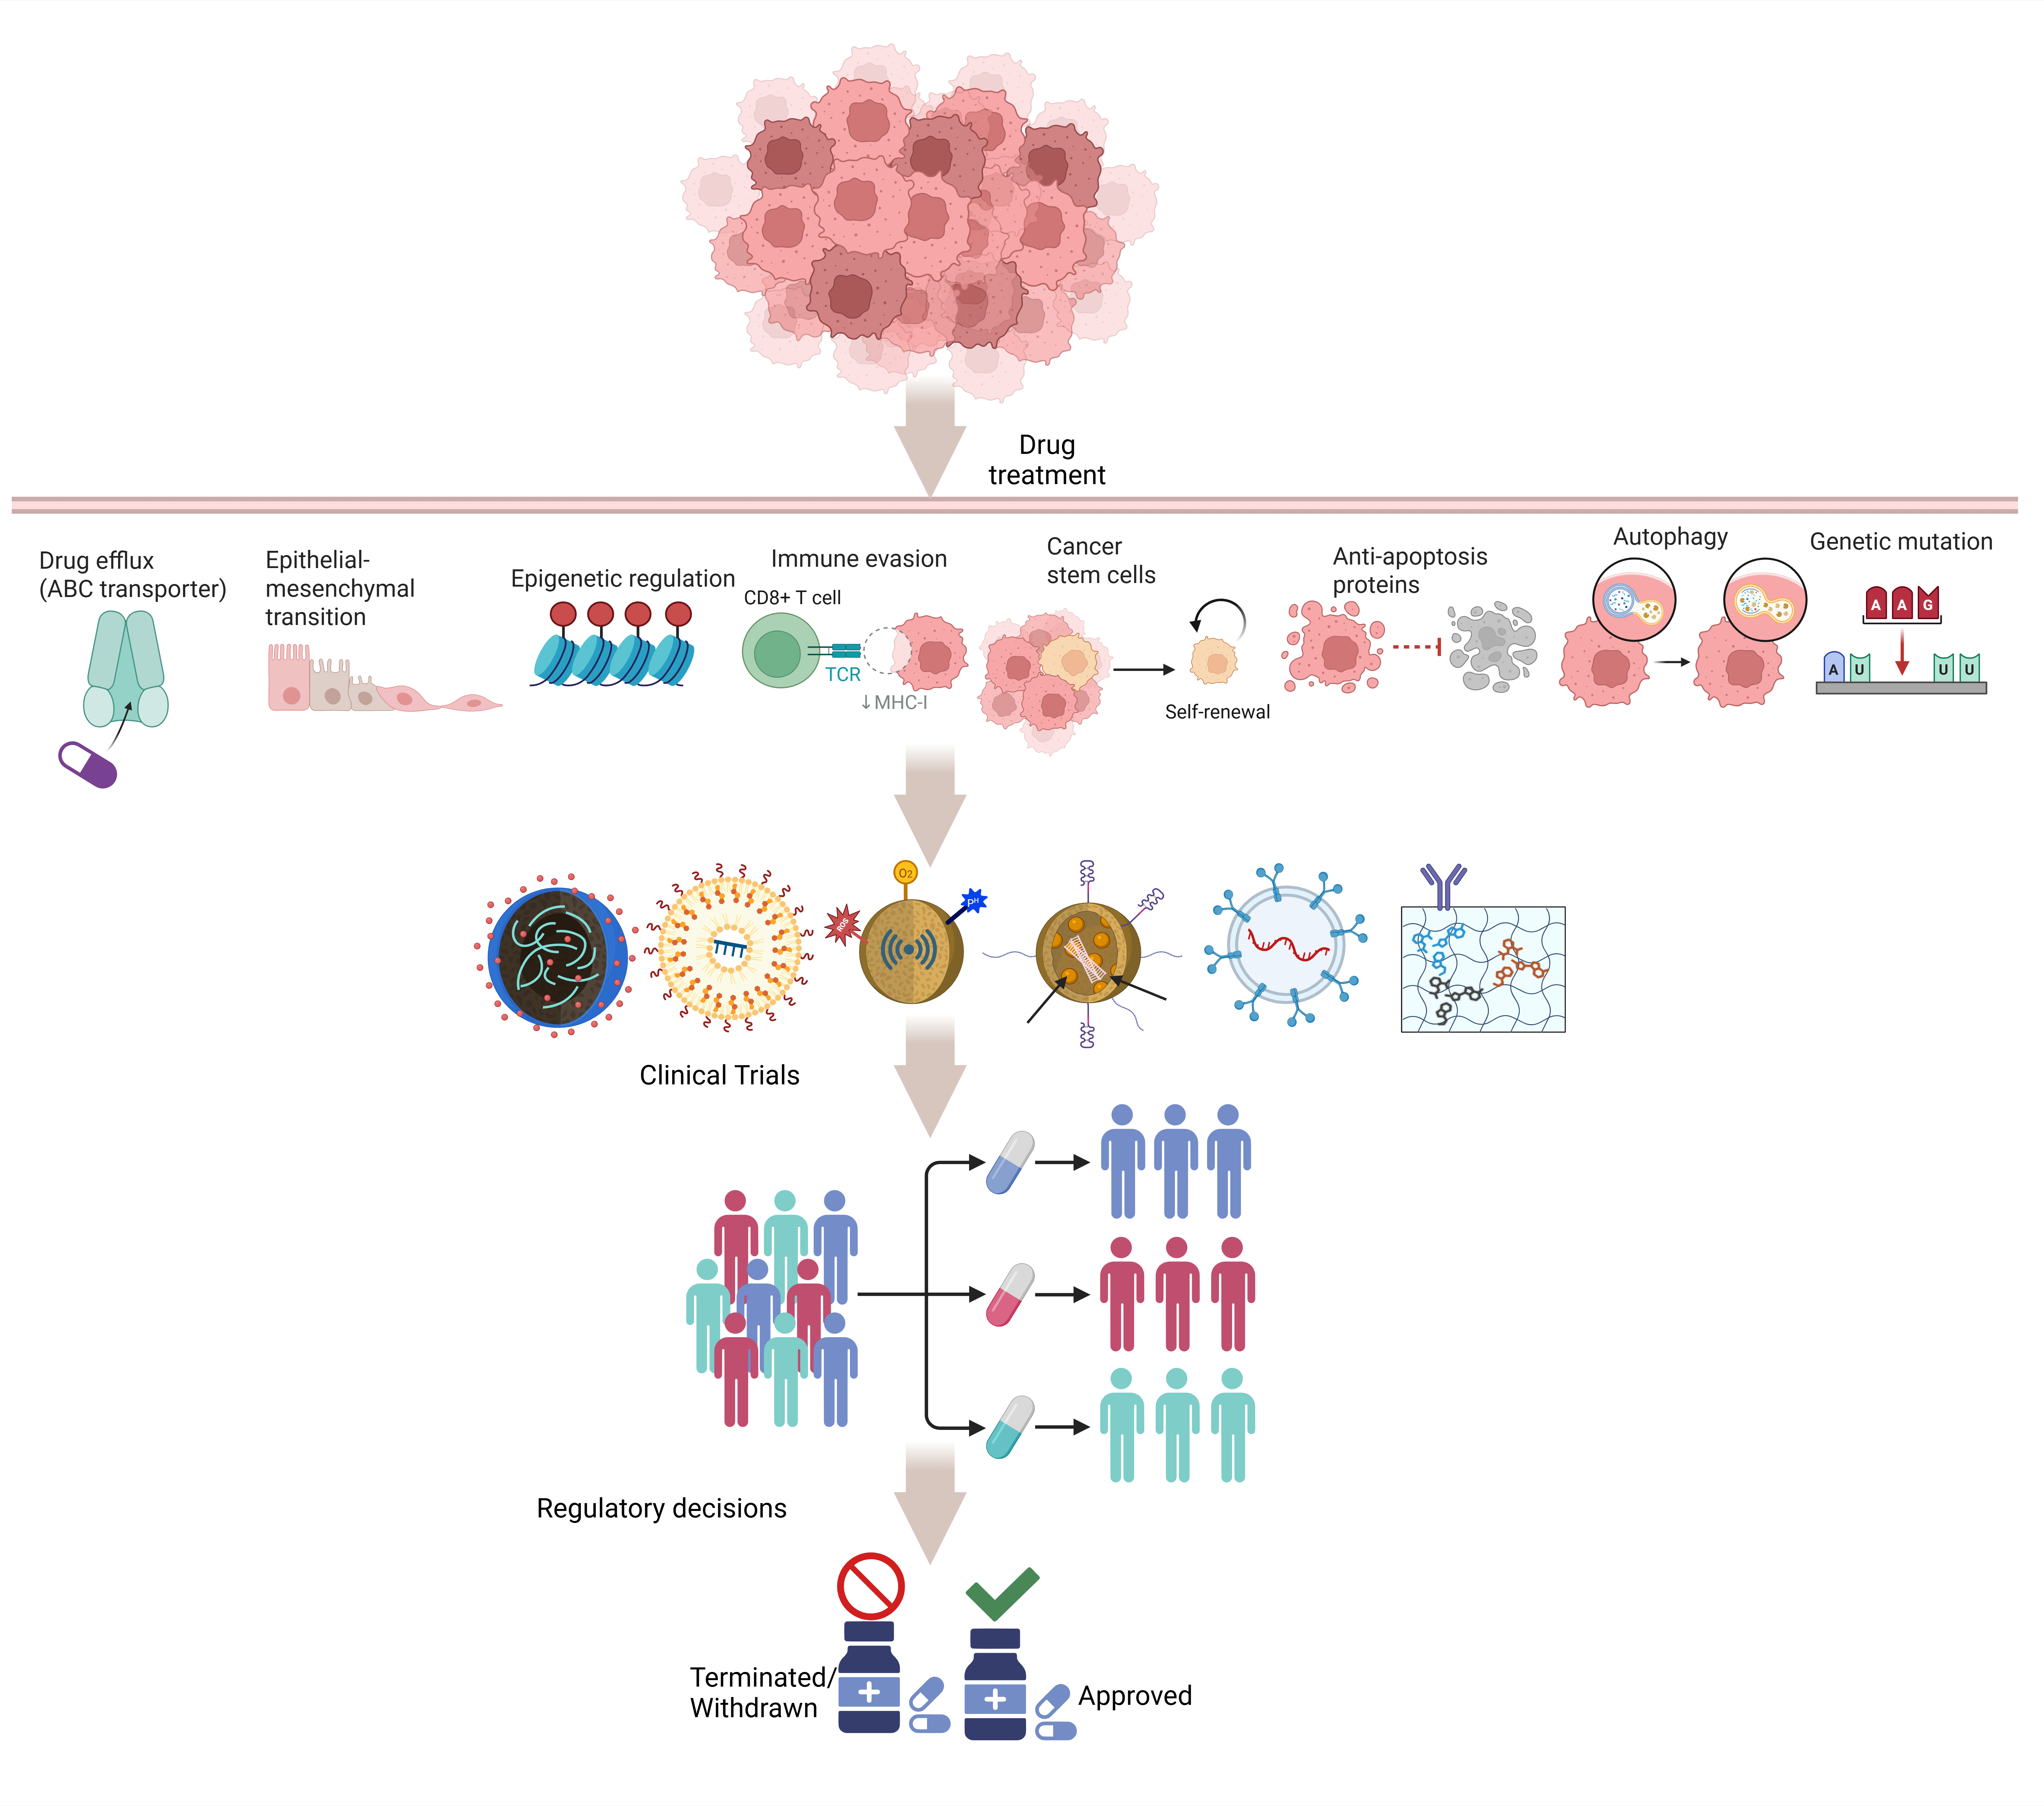

Why do promising cancer treatments sometimes fail to deliver lasting benefits?
A compelling biological target, an effective delivery system, and encouraging early results are important steps. Yet understanding a treatment’s potential also requires examining what happens when it reaches clinical testing and what can be learned when development stops or an approval is withdrawn.
Our review, published in the Journal of Experimental & Clinical Cancer Research, brings these questions together. We connect the biology of chemotherapy resistance with the clinical experience of developing treatments, examining both therapeutic opportunities and the obstacles encountered along the way.
Connecting the tumor environment with resistance
Cancer cells exist within a surrounding network of stromal cells, immune cells, blood vessels, and extracellular matrix. Low oxygen, acidity, and signals from neighboring cells can influence how cancer cells survive treatment.
Our review examines how these conditions interact with cellular signaling and epigenetic regulation, changes in gene activity that do not require changes to the DNA sequence. DNA methylation, histone modifications, and microRNA networks can help maintain resistant cellular states. These processes interact, making it important to consider how an intervention affects the wider system.
This work provides the biological foundation for the therapeutic strategies discussed throughout the article.
Where nanotechnology and gene therapy could intervene
Nanotechnology offers ways to deliver therapeutic cargo and combine agents within a delivery platform. Gene-based approaches offer tools for modifying the molecular processes that sustain resistance.
We examine these approaches alongside epigenetic treatments and combination strategies. The central question is how to match an intervention to a defined resistance mechanism while ensuring that it reaches the appropriate cells.
That requires addressing practical limitations: uneven nanoparticle accumulation, poor penetration through tumor tissue, immune clearance, gene-delivery efficiency, and potential off-target effects. A promising mechanism must be accompanied by evidence that the intended intervention can work under clinically relevant conditions.
What do clinical trials contribute to this understanding?
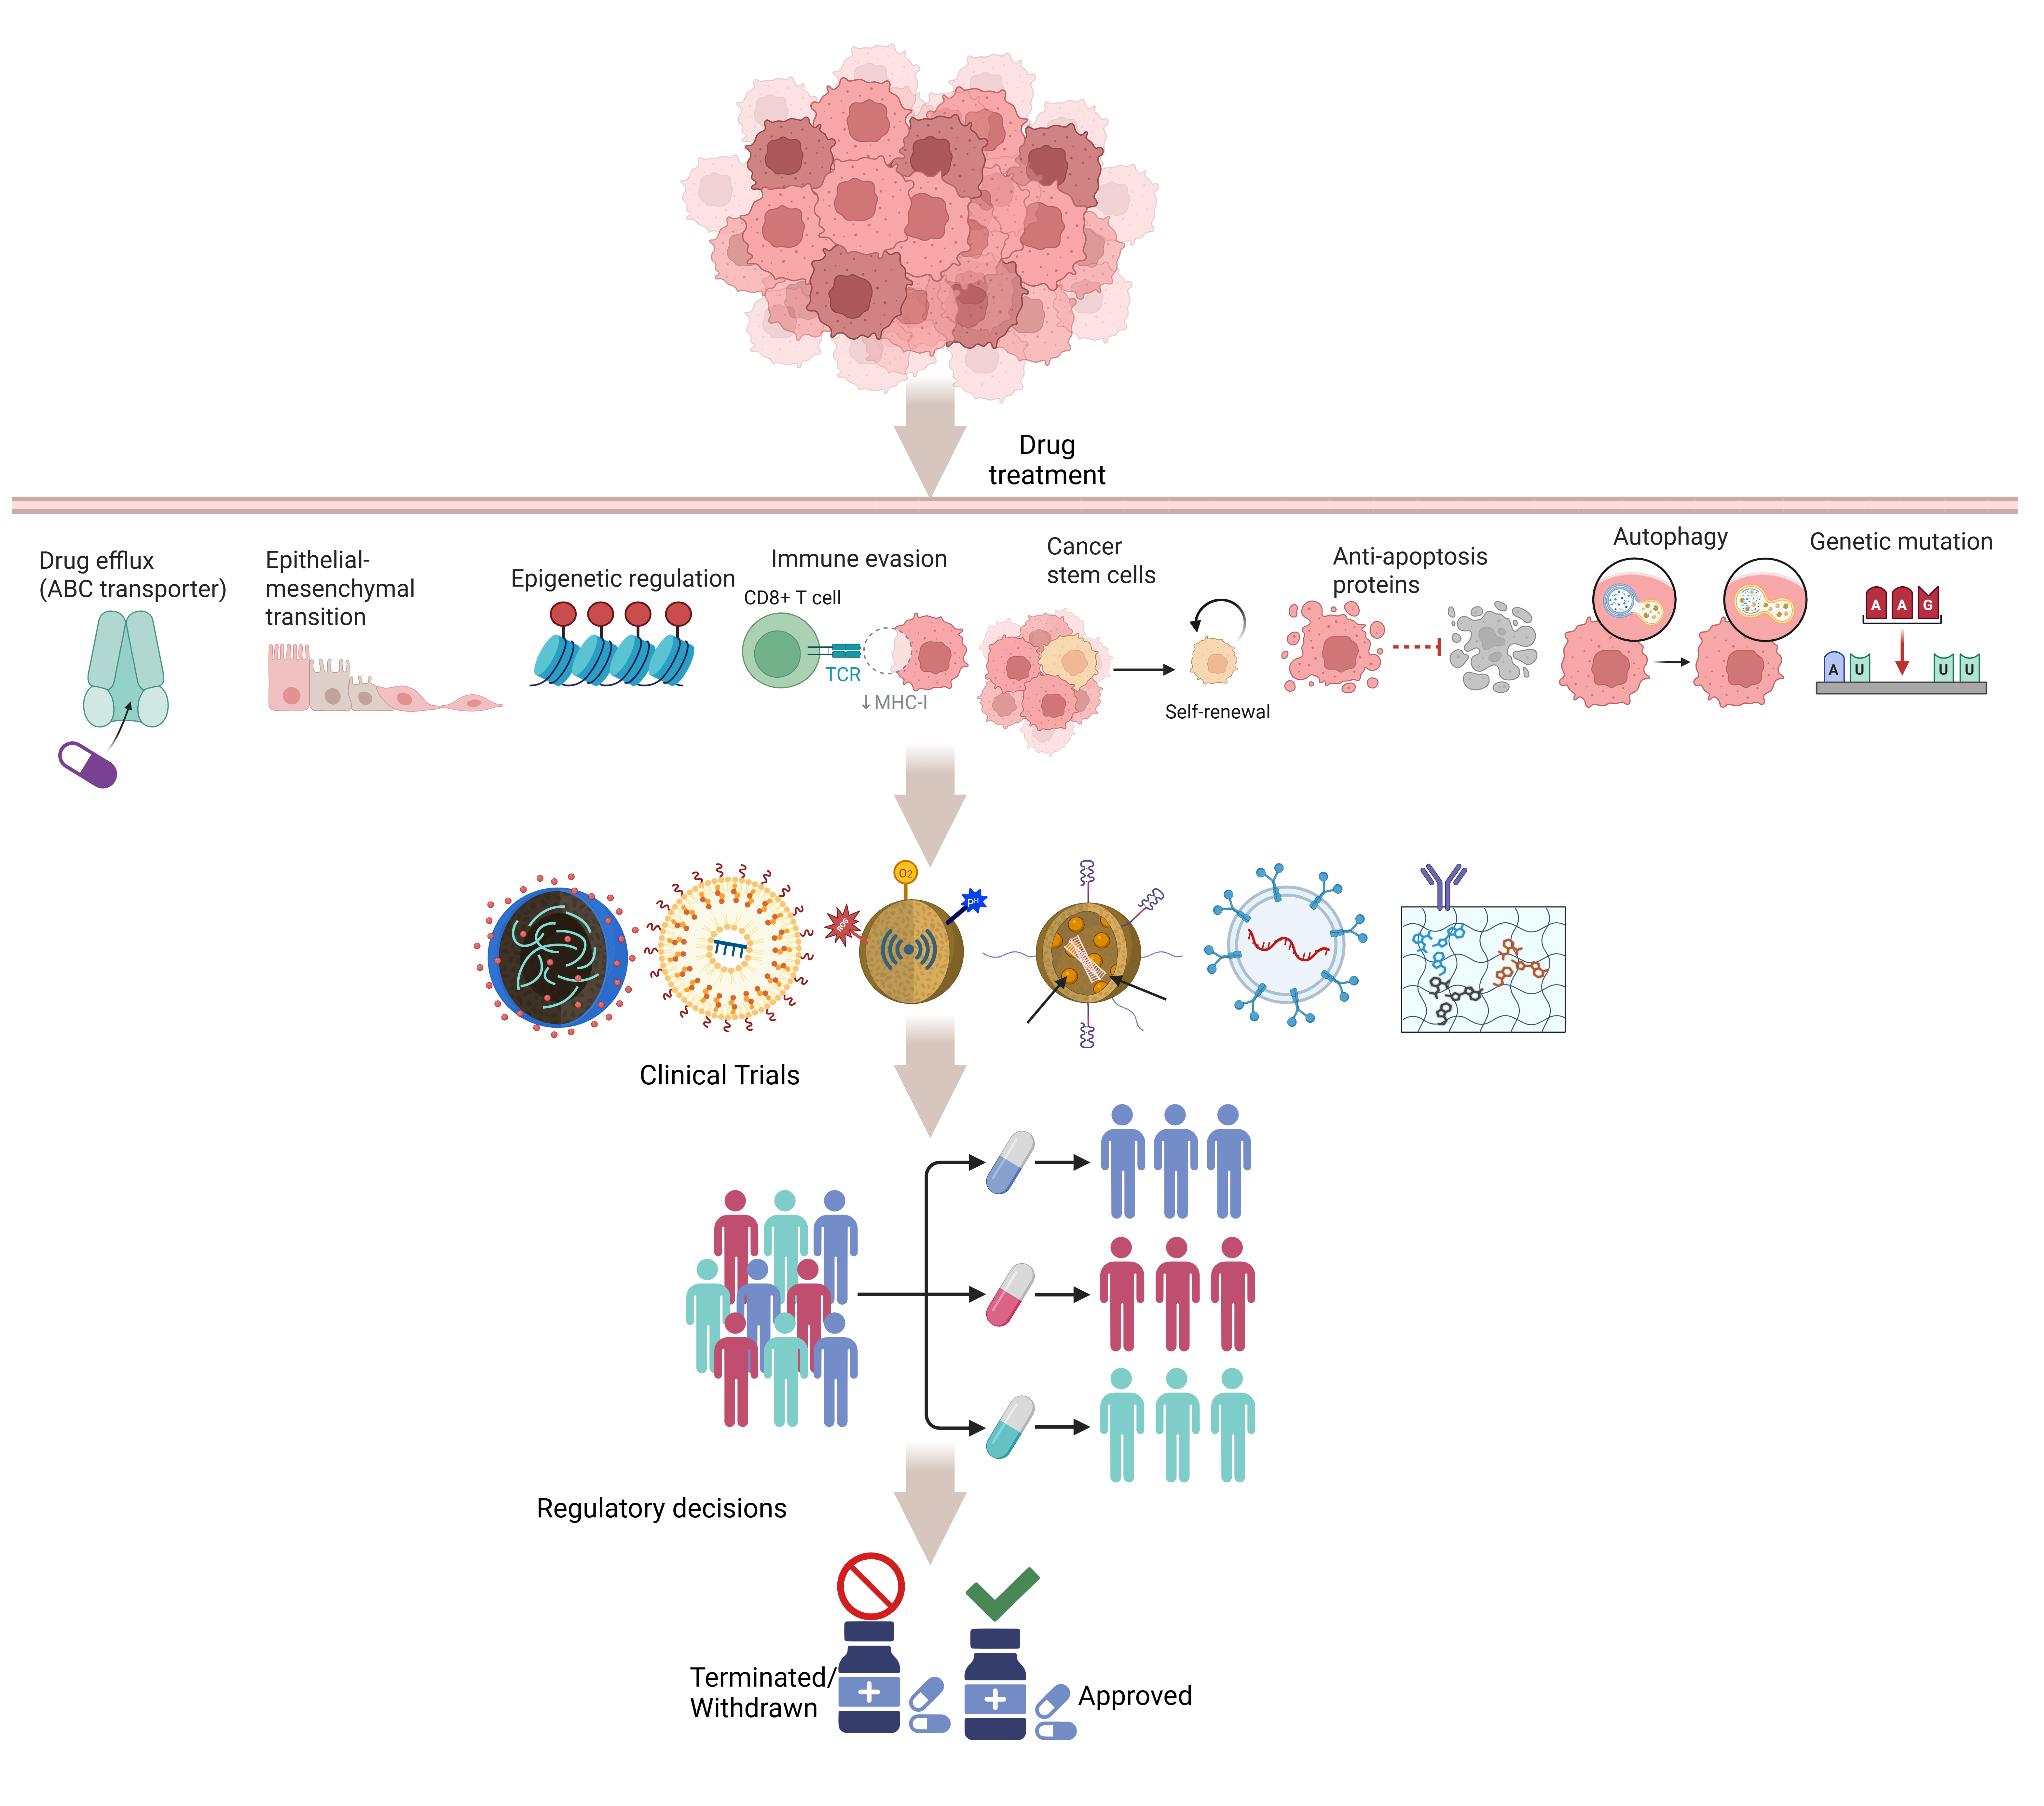
An important part of our review is its examination of clinical-trial experience across nanomedicine, gene-targeting approaches, and combination immunotherapies.
The trial summaries allow readers to consider therapeutic concepts alongside their development stage and reported outcomes. We also examine terminated or withdrawn studies and the reasons reported for stopping them, including safety concerns, insufficient efficacy, recruitment difficulties, funding interruptions, and changes in development priorities.
These distinctions matter. A completed trial does not automatically establish clinical benefit, and a terminated trial does not necessarily demonstrate that the underlying biological strategy was ineffective. Interpreting the reason for an outcome is essential to deciding what should change in the next study.
Learning from withdrawn oncology treatments
The review also examines withdrawn oncology drugs or indications and the importance of confirming benefit after initial approval.
Drug withdrawals, indication-specific withdrawals, and discontinued investigational programs represent different situations. Considering them separately helps avoid treating every setback as the same kind of failure.
For researchers, these examples raise important questions about the evidence needed to advance a treatment. Which endpoints establish meaningful benefit? How should early signals be tested? What information is needed to identify the patients most likely to respond?
These questions make clinical and regulatory experience directly relevant to experimental design.
Making resistance biology visible in treatment failure
Our review highlights a communication gap between the biological understanding of cancer resistance and how treatment failures are described. Labels such as “lack of efficacy” or “failure to confirm clinical benefit” document an outcome but can leave the underlying resistance mechanisms unexplained even where relevant molecular evidence exists.
We argue that this gap matters beyond terminology. How failures are explained can influence research priorities, funding decisions, and the design of subsequent therapies. When evidence of tumor adaptation receives insufficient attention, opportunities to develop resistance-focused treatments and predictive biomarkers may be missed.
The review calls for closer integration of molecular resistance data with clinical outcomes and regulatory summaries, greater transparency around emerging resistance mechanisms, and trial designs that account for tumor evolution.
Learning from discontinued trials and withdrawn treatments should help us identify what future therapies must address to achieve durable benefit.
Looking ahead
For me, the value of this review lies in bringing mechanistic detail, therapeutic design, clinical experience, and development setbacks into one discussion.
The resulting priorities include better biomarkers for patient selection, more representative experimental models, improved delivery, and carefully justified treatment combinations. These priorities can help researchers formulate studies that test both whether an intervention works and whether it works for the intended reason.
I am grateful to all my co-authors for their contributions. I hope the review is useful to researchers designing new platforms, clinicians following emerging treatments, and readers seeking a connected view of chemoresistance.
What should future trials measure to explain treatment failure more clearly—and help the next generation of therapies avoid repeating it?
Read the full review:
Transforming tumor microenvironments: nanotechnology and gene therapy in cellular signaling and epigenetic insight into chemoresistance
https://doi.org/10.1186/s13046-026-03720-8

Follow the Topic
-
British Journal of Cancer
This journal is devoted to publishing cutting edge discovery, translational and clinical cancer research across the broad spectrum of oncology.
-
BMC Medicine
This journal publishes outstanding and influential research in all areas of clinical practice, translational medicine, medical and health advances, public health, global health, policy, and general topics of interest to the biomedical and sociomedical professional communities.
-
Communications Biology
An open access journal from Nature Portfolio publishing high-quality research, reviews and commentary in all areas of the biological sciences, representing significant advances and bringing new biological insight to a specialized area of research.
-
Signal Transduction and Targeted Therapy
This is an international, peer-reviewed, open-access journal publishing articles related to signal transduction in physiological and pathological processes, alongside signal transduction-targeted therapeutics in the form of biological agents and small molecular drugs used to treat human diseases.
-
Journal of Cancer Survivorship
This journal publishes peer reviewed papers related to improving the understanding, prevention, and management of multiple areas related to cancer survivorship that can affect quality care, symptom management, function, and well-being.
-
Clinical and Experimental Medicine
-
Prostate Cancer and Prostatic Diseases
This journal covers all aspects of prostatic diseases, in particular prostate cancer, the subject of intensive basic and clinical research world-wide.
-
Cancer Nanotechnology
This is a peer-reviewed, open access journal aiming to disseminate cutting-edge research and promote emerging trends in the use of nanostructures and the induction of nanoscale processes for the prevention, diagnosis, treatment of cancer.
-
Cancer and Metastasis Reviews
-
Cancer Cell International
This journal publishes articles on all aspects of cancer cell biology originating from work using laboratory experimentation.
-
Journal of Experimental & Clinical Cancer Research
Journal of Experimental & Clinical Cancer Research is an online peer-reviewed journal that publishes original research papers, reviews and commentaries in cancer research, from bench to bedside.
-
Molecular Cancer
This journal promotes the exchange of ideas, concepts and findings in any area of cancer and related biomedical science, from a molecular point of view.
-
Cancer Chemotherapy and Pharmacology
-
Cancer Gene Therapy
The essential gene and cellular therapy resource for cancer researchers and clinicians, keeping readers up to date with the latest developments in gene and cellular therapies for cancer.
-
A Collection of original research articles that highlight cutting-edge research on TME crosstalk and its therapeutic implications.














Related Collections
With Collections, you can get published faster and increase your visibility.
Polyploid giant cancer cells
Publishing Model: Open Access
Deadline: Ongoing
Treatment and management of MASH/MASLD
BMC Medicine is calling for submissions to our new Collection focused on the treatment and management of Metabolic Dysfunction-Associated Steatotic Liver Disease (MASLD) and Metabolic Dysfunction-Associated Steatohepatitis (MASH). We welcome research that explores the pathophysiology, diagnostics, therapeutic interventions, and clinical outcomes related to these increasingly prevalent liver diseases, aiming to enhance understanding and improve patient care in this vital area of public health.
MASLD represents a broad spectrum of liver disease that is increasingly recognized as a major contributor to global morbidity. MASH is the progressive inflammatory form of MASLD and is associated with an increased risk of adverse cardiometabolic and liver-related outcomes such as fibrosis, cirrhosis, and hepatocellular carcinoma (HCC). As the prevalence of obesity, diabetes, and metabolic syndrome continues to rise worldwide, the burden of MASLD is expected to increase substantially, necessitating a deeper understanding of its pathophysiology, prevention, and management.
The recent redefinition of nonalcoholic fatty liver disease (NAFLD) as MASLD has reshaped the clinical and biological framework of Steatotic Liver Disease (SLD) by placing cardiometabolic dysfunction at the center of disease classification. MASLD is now defined as hepatic steatosis in the presence of at least one cardiometabolic risk factor, including overweight or obesity, impaired glucose tolerance or type 2 diabetes, low HDL cholesterol, hypertriglyceridemia, and hypertension. This updated nomenclature has important implications not only for clinical practice, but also for research, as it highlights the need to better characterize molecular, metabolic, and clinical signatures underlying disease heterogeneity. In this context, a major challenge is to disentangle the contribution of liver-specific disease mechanisms from those related to cardiometabolic comorbidities in order to identify more precise biomarkers, improve patient stratification, and refine risk prediction across the MASLD spectrum. Current research is shedding light on the complex interplay between metabolic dysfunction, liver inflammation, fibrosis progression, and extrahepatic complications, while also exploring emerging biomarkers, diagnostic tools, and therapeutic strategies.
Addressing MASLD is crucial not only for individual patient outcomes but also for public health on a broader scale. Recent advances in pharmacological treatments, lifestyle interventions, and precision medicine are opening new opportunities for the management of MASLD across both early and advanced disease stages. These developments underscore the need for ongoing research to optimize treatment strategies and to enhance early detection and diagnosis, which are pivotal for improving patient care and reducing the overall healthcare burden associated with SLD.
As research in this field continues to evolve, we may anticipate significant breakthroughs in the understanding molecular mechanisms underlying MASLD forms. Future studies could lead to the identification of novel therapeutic targets, innovative biomarkers for early diagnosis, and personalized treatment approaches that cater to the unique metabolic profiles of patients. Such advancements have the potential to revolutionize the management of SLD and improve patient outcomes on a global scale.
Topics of interest include but are not limited to:
- Understanding the pathophysiology of the MASLD spectrum, with particular focus on MASH and the advanced stages (fibrosis, cirrhosis, and HCC)
- Identification of molecular, metabolic, and clinical signatures associated with disease heterogeneity and progression, including the impact of the new MASLD definition on patients’ stratification
- Biomarkers discovery and new diagnostic/prognostic tools for MASLD monitoring, especially for high-risk categories (such as patients with type 2 diabetes)
- New translational, pharmacological, and lifestyle-based interventions for the MASLD spectrum
- Clinical outcomes and extrahepatic complications in patients with MASLD/MASH
- Pathogenesis and clinical implications of multi-organ crosstalk in MASLD/MASH, including liver-heart, liver-kidney, and adipose-liver axes, and their mechanistic contribution to systemic metabolic dysfunction
- The public health implications, with specific attention to health systems and epidemiology, of the increased prevalence of MASLD/MASH
- MASLD in the context of liver transplantation, encompassing pre-transplant evaluation, post-transplant recurrence, and implications of donor steatosis
All manuscripts submitted to this journal, including those submitted to collections and special issues, are assessed in line with our editorial policies and the journal’s peer review process. Reviewers and editors are required to declare competing interests and can be excluded from the peer review process if a competing interest exists.
This Collection supports and amplifies research related to SDG 3 (Good Health and Well-being).
Publishing Model: Open Access
Deadline: Jan 29, 2027


