A mixed methods study of using Wasta in healthcare services in Palestine: predictors, consequences and proposed solutions
Published in Business & Management

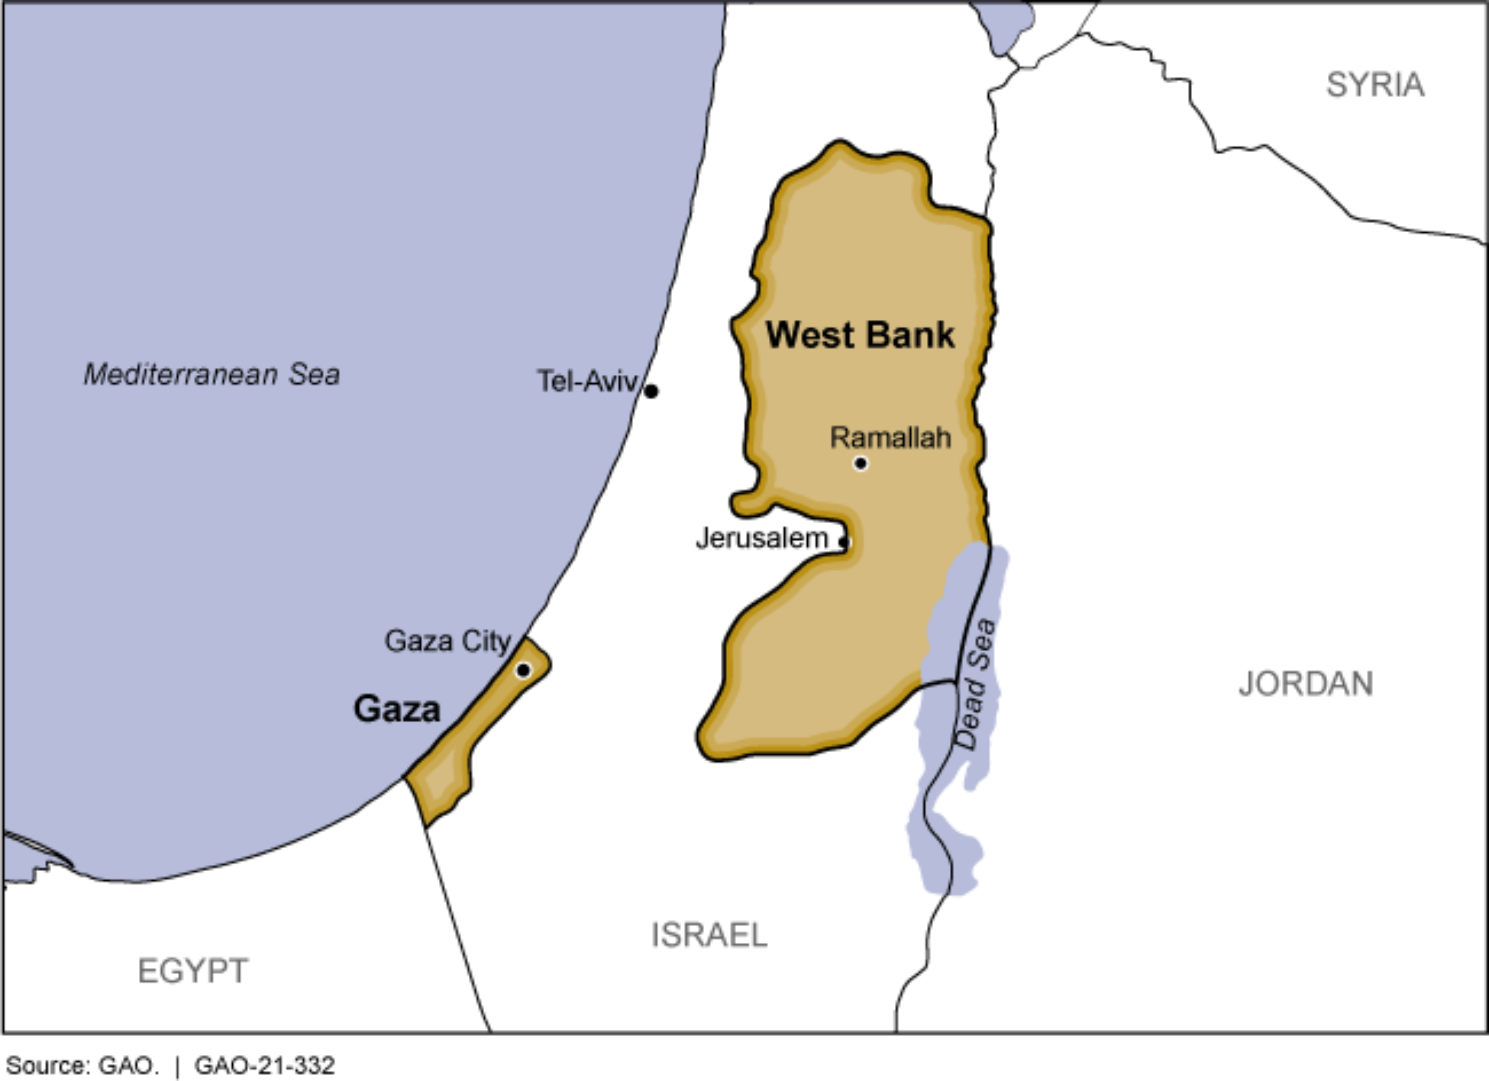

This unique study conducted in 2021-22 in the occupied Palestinian territories and Gaza examined the use of wasta. Examining the use of wasta in healthcare in Palestine, we employed qualitative (ten health professionals and eighteen patients from Gaza and the West Bank) and quantitative research methods, surveying more than 700 individuals. Where the official processes to reach a goal are corrupt, bureaucratic, or inefficient persons often turn to using wasta to overcome barriers.
Participants included refugees living in camps, urban, and rural dwellers from the age of 18. Approximately one-third (34%) stated they used wasta to get a health service in the last year, 39.3% from Gaza and 31.6% from the West Bank. Wasta is reportedly also used within healthcare institutions by some employees to gain unfair advantages over others. Our interviews also highlighted social and organizational-level predictors and consequences of wasta. The potential predictors include scarcity of resources (material, human, and financial), cultural factors, and inefficient administration. The consequences of wasta include inequities in healthcare, decreased healthcare professionals’ motivation and morale, and lower service quality.
This study considerably enriched the conceptual definition of wasta use in healthcare settings by elucidating the multifaceted mechanisms through which it manifests, its predictors, and its consequences. Wasta can be employed by utilizing social connections, political affiliations, family ties, and economic means. This study confirmed previous research about the role of organizational, social, and economic factors in causing wasta.
The utilization of wasta in healthcare leads to outcomes such as disparities, reduced staff motivation, and compromised service quality. Through wasta and social connections, some patients may gain unfair advantages over others. Our interviews revealed that when staff are promoted and rewarded through wasta or social connections rather than for hard work, dedication, or performance, inequities become manifest. These unfair practices cast a negative shadow on the institution and its services by eroding the morale and motivation of its personnel.
Predictors and consequences of wasta in countries where official processes to reach a goal are corrupt, bureaucratic, or inefficient, individuals resort to wasta to overcome oppressive processes [1]. Patriarchy, tribalism, religious and political strife, inequities, discrimination, and lack of trust in public institutions are contextual vices within which wasta proliferates [2, 3].
The higher prevalence of wasta in refugee camps and in Gaza is probably because these communities have faced disadvantages for generations, enduring various difficulties and injustices. It is possible that their perception, based on personal experiences or hearsay, is that utilizing wasta can help improve their situation. In the camps, residents are bound by a common history of forced displacements and are living in crowded conditions. Political activism is stronger in camps.
Wasta results in inequalities by depriving women and those with lower social networks from accessing opportunities [4, 5]. Wasta encourages people to invest more in social networks rather than other more useful forms of social capital [6]. Wasta could decrease the utilization of healthcare services via a lack of trust in the system. Additionally, wasta may lower healthcare providers’ motivation, satisfaction, and morale. Our interviews highlighted social and organizational-level predictors and consequences of wasta. The consequences of wasta include inequities in healthcare, decreased healthcare professionals’ motivation and morale, and lower service quality.
It is essential to optimize processes for efficiency, alleviate financial strains, and implement accountability measures in the healthcare domains.
- Horak S, Afiouni F, Bian Y, Ledeneva A, Muratbekova-Touron M, Fey CF. Informal networks: Dark sides, bright sides, and unexplored dimensions. Manag Organ Rev. 2020;16:511–42.
- Hutchings K, Weir D. Guanxi and Wasta: A comparison. Thunderbird Int Bus Rev. 2006;48:141–56.
- Alsarhan F, Ali S, Weir D, Valax M. Impact of gender on use of wasta among human resources management practitioners. Thunderbird Int Bus Rev. 2021;63:131–43.
- Abalkhail JM, Allan B. “Wasta” and women’s careers in the Arab Gulf States. Gend Manag Int J. 2016;31:162–80.
- Banihani M. Empowering Jordanian women through entrepreneurship. J Res Mark Entrep. 2020;22:133–44.
- Baranik L, Gorman B, Wright N. Wasta and its relationship to employment status and income in the Arab Middle East. Curr Sociol. 2021;:00113921211024705.
Follow the Topic
-
BMC Health Services Research
An open access, peer-reviewed journal that considers articles on all aspects of health services research, focusing on digital health, governance, policy, system quality and safety, delivery and access, financing and economics, implementing reform, and the workforce.

Related Collections
With Collections, you can get published faster and increase your visibility.
Strengthening health system resilience: from emergency preparedness to response and recovery
Health systems worldwide are increasingly facing the dual challenges of rising health demands and the unpredictability of emergencies. Recent and ongoing polycrises—whether the COVID-19 pandemic, sporadic outbreaks of emerging or reemerging diseases, or increasingly frequent emergencies resulting from natural hazards—have highlighted the urgent and compelling need for enhanced health system preparedness and resilience. Effective emergency preparedness involves not only robust planning and response strategies but also the capability to adapt and recover quickly from disruptions. This Collection aims to explore the multifaceted aspects of strengthening health systems to ensure they can effectively prepare for, respond to, and recover from emergencies and maintain continuity of care.
Addressing the resilience of health systems is crucial for safeguarding public health and ensuring that healthcare providers can deliver effective services during crises. Recent advancements have included the integration of technology in health management, improved supply chain logistics, and enhanced workforce training. Furthermore, frameworks for assessing health system resilience have been developed, offering valuable insights into best practices. However, ongoing research is needed to evaluate the effectiveness of these strategies and to implement innovative solutions that can be adapted to various contexts and crises.
Topics for submission but are not limited to:
- Governance, leadership, and policy approaches for resilient health systems
- Frameworks and metrics for assessing and strengthening health system preparedness and resilience
- Financing mechanisms and economic resilience of health systems in emergencies
- Community engagement and locally led strategies in crisis preparedness, response and recovery
- Workforce training, surge capacity, and capability building for emergency response
- Supply chain management and essential resource security during emergencies
- Digital technologies and data-driven innovations for emergency preparedness, response and recovery
- Health system resilience in underserved, vulnerable, or fragile settings
This Collection supports and amplifies research related to SDG 3: Good Health and Well-being.
All manuscripts submitted to this journal, including those submitted to collections and special issues, are assessed in line with our editorial policies and the journal’s peer review process. Reviewers and editors are required to declare competing interests and can be excluded from the peer review process if a competing interest exists.
Publishing Model: Open Access
Deadline: Mar 19, 2027
Strengthening private and public health insurance models for affordability of health services and financial protection
The rising costs of healthcare and the increasing burden of out-of-pocket expenses have underscored the need for effective health insurance models that promote financial protection and affordability. This Collection aims to explore innovative approaches to strengthen both private and public health insurance systems, focusing on risk pooling, equitable access, and coverage expansion. By examining various insurance frameworks, we aim to understand how they can better serve populations, particularly in low- and middle-income countries where catastrophic health expenditures are prevalent.
Advancements in health insurance models have demonstrated the potential to significantly reduce financial barriers to healthcare access, contributing to improved health outcomes. Research has shown that effective risk pooling mechanisms and the implementation of universal health coverage (UHC) can mitigate catastrophic health expenditures and enhance the quality of healthcare services. As health systems worldwide face increasing pressures, it is crucial to identify and share best practices that ensure equitable access to essential health services while maintaining financial sustainability.
Topics for submission:
- Strategies for cost reduction in health insurance
- Addressing catastrophic health expenditure through insurance
- Reducing out-of-pocket costs for vulnerable populations
- Enhancing risk pooling for equitable access
- Advancing universal health coverage (UHC) initiatives
This Collection supports and amplifies research related to SDG 3 (Good Health and Well Being).
All manuscripts submitted to this journal, including those submitted to collections and special issues, are assessed in line with our editorial policies and the journal’s peer review process. Reviewers and editors are required to declare competing interests and can be excluded from the peer review process if a competing interest exists.
Publishing Model: Open Access
Deadline: Dec 11, 2026