Regulation of Human Genome Editing in Singapore
Published in Social Sciences, Genetics & Genomics, and Public Health


Please refer to the following journal articles:
Stringent criteria needed for germline genome editing of human IVF embryos
Genome Editing Should Preferably Be Carried Out on Fetuses In Utero Rather Than IVF Embryos
Do not overlook the possibility of genome-edited somatic cells ending up in the human germline
Please also listen to the audio podcast:
Key aspects of how human genome editing should be regulated include:
-
Establishing International Regulatory Frameworks and Oversight
◦ International bodies like the World Health Organization (WHO) should establish standing committees to draft rigorous and comprehensive international regulatory frameworks.
◦ These frameworks must provide strict oversight on human genome editing for both experimental and therapeutic applications.
◦ Particular tight governance should be imposed on the transmission of genetic modifications to the human germline.
◦ Regulators at all levels need to actively review and adapt current ethical guidelines and laws to keep pace with scientific advances, formulating clear and unambiguous directives.
◦ The international regulatory framework must specifically account for the plausible chance of genome-edited somatic cells ending up in the human germline, whether intentionally or inadvertently, through various new technology platforms.
-
Principles for Application and Decision-Making
◦ Regulations should be based on core medical ethics principles, including non-maleficence (minimizing harm) and autonomy (ensuring informed consent).
◦ Rigorous and comprehensive counseling must be provided to prospective parents with known genetic mutations, enabling informed consent and autonomous decision-making when choosing between fetal or embryo genome editing. This counseling must cover pertinent safety risks and available alternatives.
◦ There must be a clear distinction in future legislation between preventing genetic diseases and human enhancement. Recognizing that these boundaries can be blurred, intensive dialogue among medical doctors, scientists, bioethicists, and lawmakers is essential for delineation and clarification.
◦ Regulations should consider sociocultural factors in different countries, where alternatives like gamete/embryo donation or child adoption may not be culturally acceptable. In such cases, germline genome editing of IVF embryos might be permitted under strictly limited and tightly regulated conditions, as a last resort.
-
Regulation of Germline Genome Editing of IVF Embryos
◦ This type of editing is controversial because it is not directly health or lifesaving, but rather intended to prevent genetic diseases in future offspring, and carries substantial medical risks.
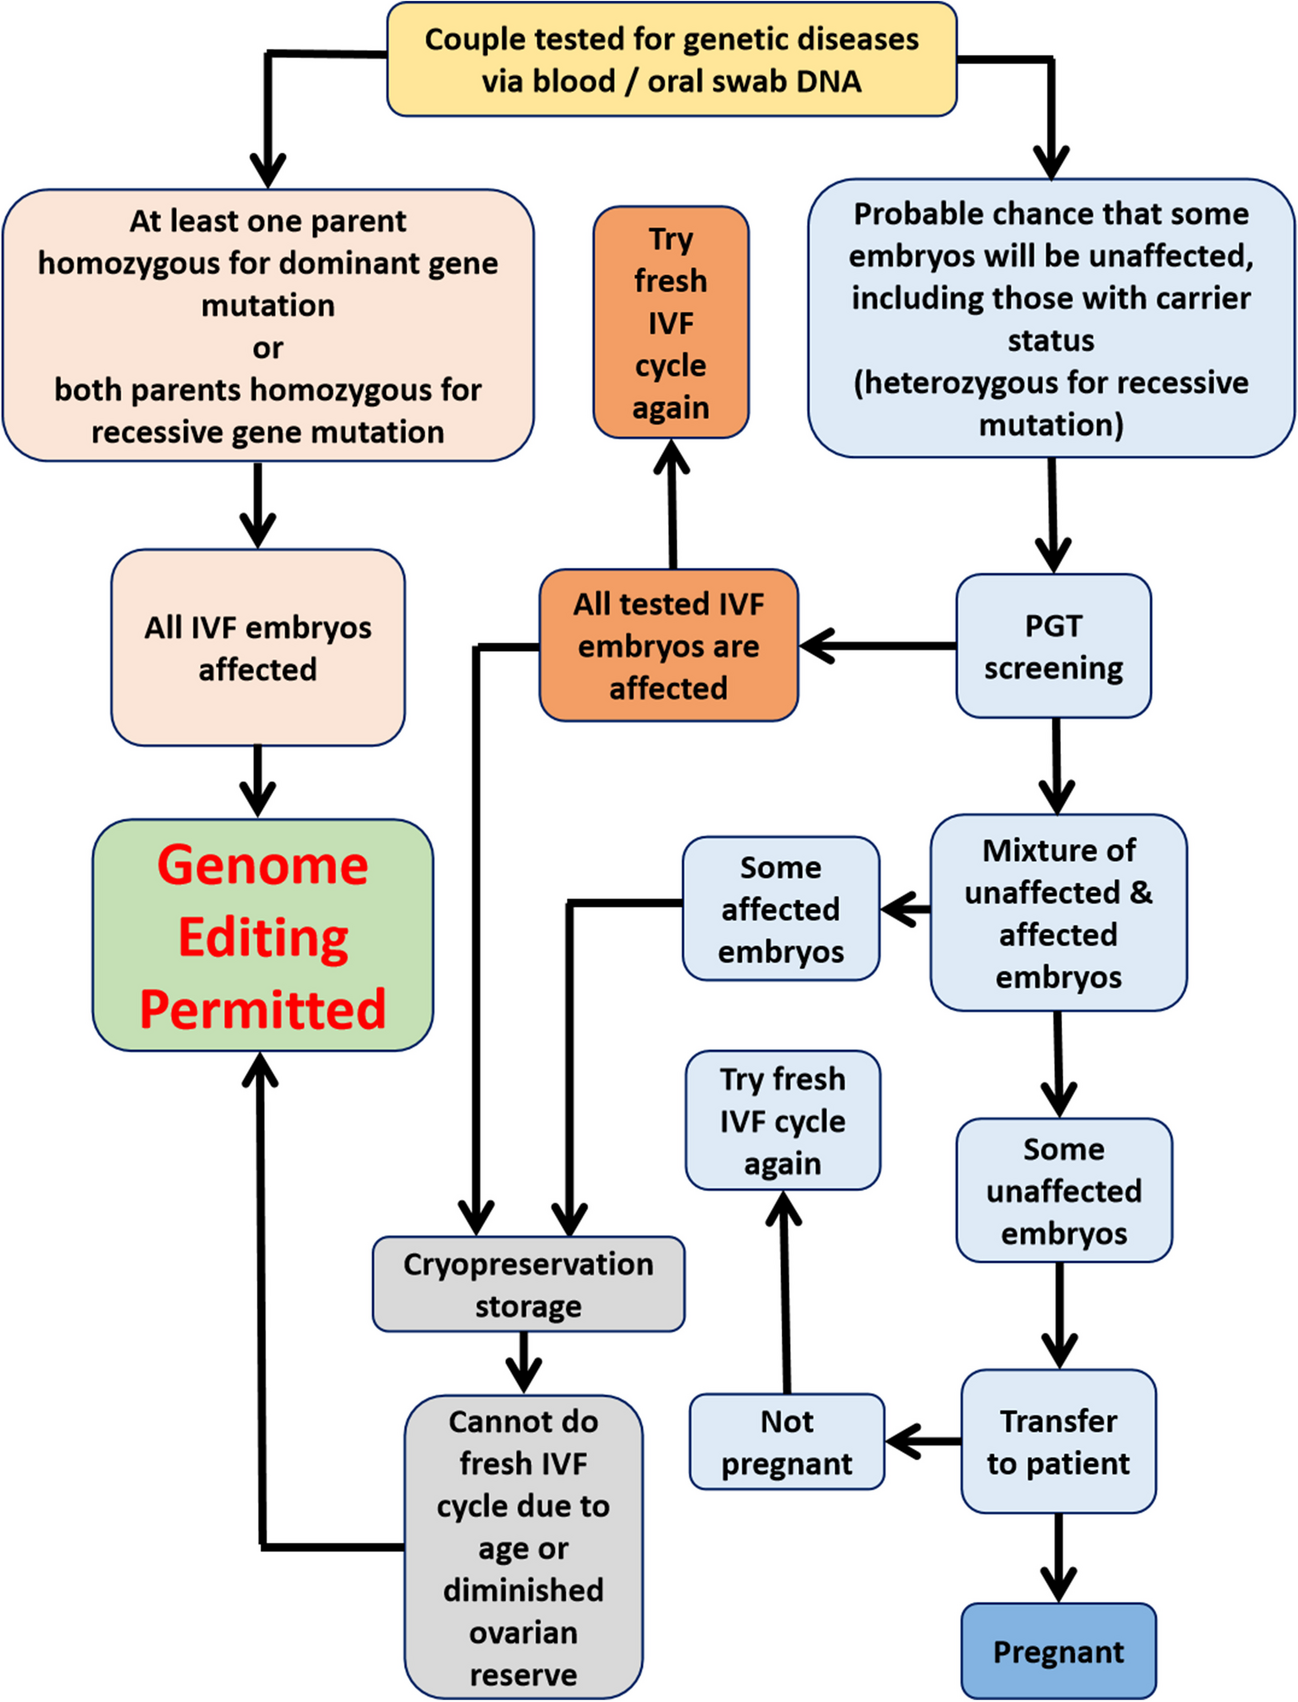
◦ Stringent criteria are proposed for future clinical trials, primarily based on the principle of non-maleficence:
▪ It should be cautiously and judiciously applied, avoiding non-essential usage.
▪ If there is a fair chance that some IVF embryos will not be affected by genetic diseases, initial preimplantation genetic testing (PGT) screening must be performed to identify unaffected embryos for transfer.
▪ IVF embryos with carrier status (heterozygous for a recessive gene mutation) should not undergo germline genome editing to avoid unnecessary risks, as they can still result in an unaffected child.
▪ If patients fail to conceive after transferring unaffected embryos, they should be encouraged to undergo another fresh IVF cycle rather than opting for genome editing of remaining affected embryos.
▪ Genome editing of remaining affected embryos should only be permitted as a last resort, if the patient is unable to produce any more unaffected embryos in a fresh IVF cycle due to advanced maternal age or diminished ovarian reserves.
◦ There should be rigorous pre-clinical data from multi-generational animal studies to better understand the effects on future generations before such procedures are widely adopted.
◦ Worldwide regulatory bans should be imposed on the utilization of mosaic chimeric preimplantation embryos in clinical assisted reproduction due to increased risks of cancer and autoimmune diseases. Regulations should specify that genome-edited somatic cells or their induced pluripotent stem cell (iPSC) derivatives can only be used for gene therapy past a specific developmental stage beyond preimplantation embryos, to minimize germline infiltration.
-
Regulation of Fetal Genome Editing In Utero
◦ Fetal genome editing is considered less ethically contentious than embryo genome editing because it typically does not involve man-made genetic modifications transmitted to future generations.
◦ However, concerns exist that genome editing performed on fetal somatic cells in utero may unintentionally transmit to germline tissues due to the high plasticity and extensive tissue remodeling during fetal gestation.
◦ This possibility necessitates rigorous postpartum genetic screening and testing of offspring of fetal gene therapy. However, current methods for detecting genome-edited cells in the germline may require invasive and potentially destructive biopsies for sexually mature females.
◦ Amendments to relevant healthcare regulations may be required to enable patients to opt for genome editing of fetuses in utero as an alternative therapy to IVF embryo editing, especially if restrictive legislation on transferring affected IVF embryos remains in place.
◦ Genome editing of surgically-extracted fetal somatic cells followed by subsequent re-transplantation back to the fetus in utero may represent a better strategy for avoiding heritable genome editing errors and unknown detrimental effects.
Follow the Topic
-
Journal of Assisted Reproduction and Genetics
This journal publishes cellular, molecular, genetic, and epigenetic discoveries advancing our understanding of the biology and underlying mechanisms from gametogenesis to offspring health.
