Symptoms and respiratory infections: Insights from the UK 2022/2023 winter season
Published in Public Health and Statistics

Ever wondered about the likelihood of having the flu if you’ve got a fever? Or how your age influences the symptoms you experience if ill with RSV? And can we distinguish SARS-CoV-2 from other respiratory infections based on which symptoms people report? These are some of the questions our recent research study explored. In this blog post, I’ll explain the motivation behind our study and highlight our key findings.
What was our study about?
Respiratory infections affect lots of people every winter, and cause symptoms such as sneezing or fever. Often, these symptoms are mild, but such infections can also lead to more serious illness. Understanding how many people are getting different respiratory infections over time, and what symptoms they experience, is important to accurate diagnosis and effective treatment in the NHS. Getting more knowledge about these infections can also aid healthcare preparedness and inform vaccination policies.
Influenza A/B (flu) and respiratory syncytial virus (RSV) are two common causes of respiratory infection. Since the start of the COVID-19 pandemic, SARS-CoV-2 has also been co-circulating with these viruses. Our recent study investigated these three respiratory infections in the UK during the 2022-2023 winter season, along with self-reported symptoms. This study was based on a large household survey, the Office of National Statistics COVID-19 Infection Survey. Around 750 participants in the survey were randomly selected each week to have their nose and throat swabs PCR-tested for flu, RSV, and SARS-CoV-2. Our research study analysed this data using a range of statistical methods, including generalised additive models, which is a type of regression model.
What were the main findings?
Our study found that differentiating between flu, RSV, and SARS-CoV-2 based on symptoms alone may prove difficult. Symptom profiles were largely similar across the three viruses, with middle-aged participants being more likely to report symptoms than other age groups. Cough, sore throat, sneezing, and fatigue were amongst the most common symptoms for all three infections.
We did however see some differences between the three infections. For instance, RSV-positive people in our study generally reported fewer symptoms than those who tested positive for SARS-CoV-2 or the flu. In particular, fever was relatively uncommon amongst those with RSV. Importantly, we also observed considerable background rates of several symptoms, especially cough in young children, and fatigue and headache in middle-aged participants.
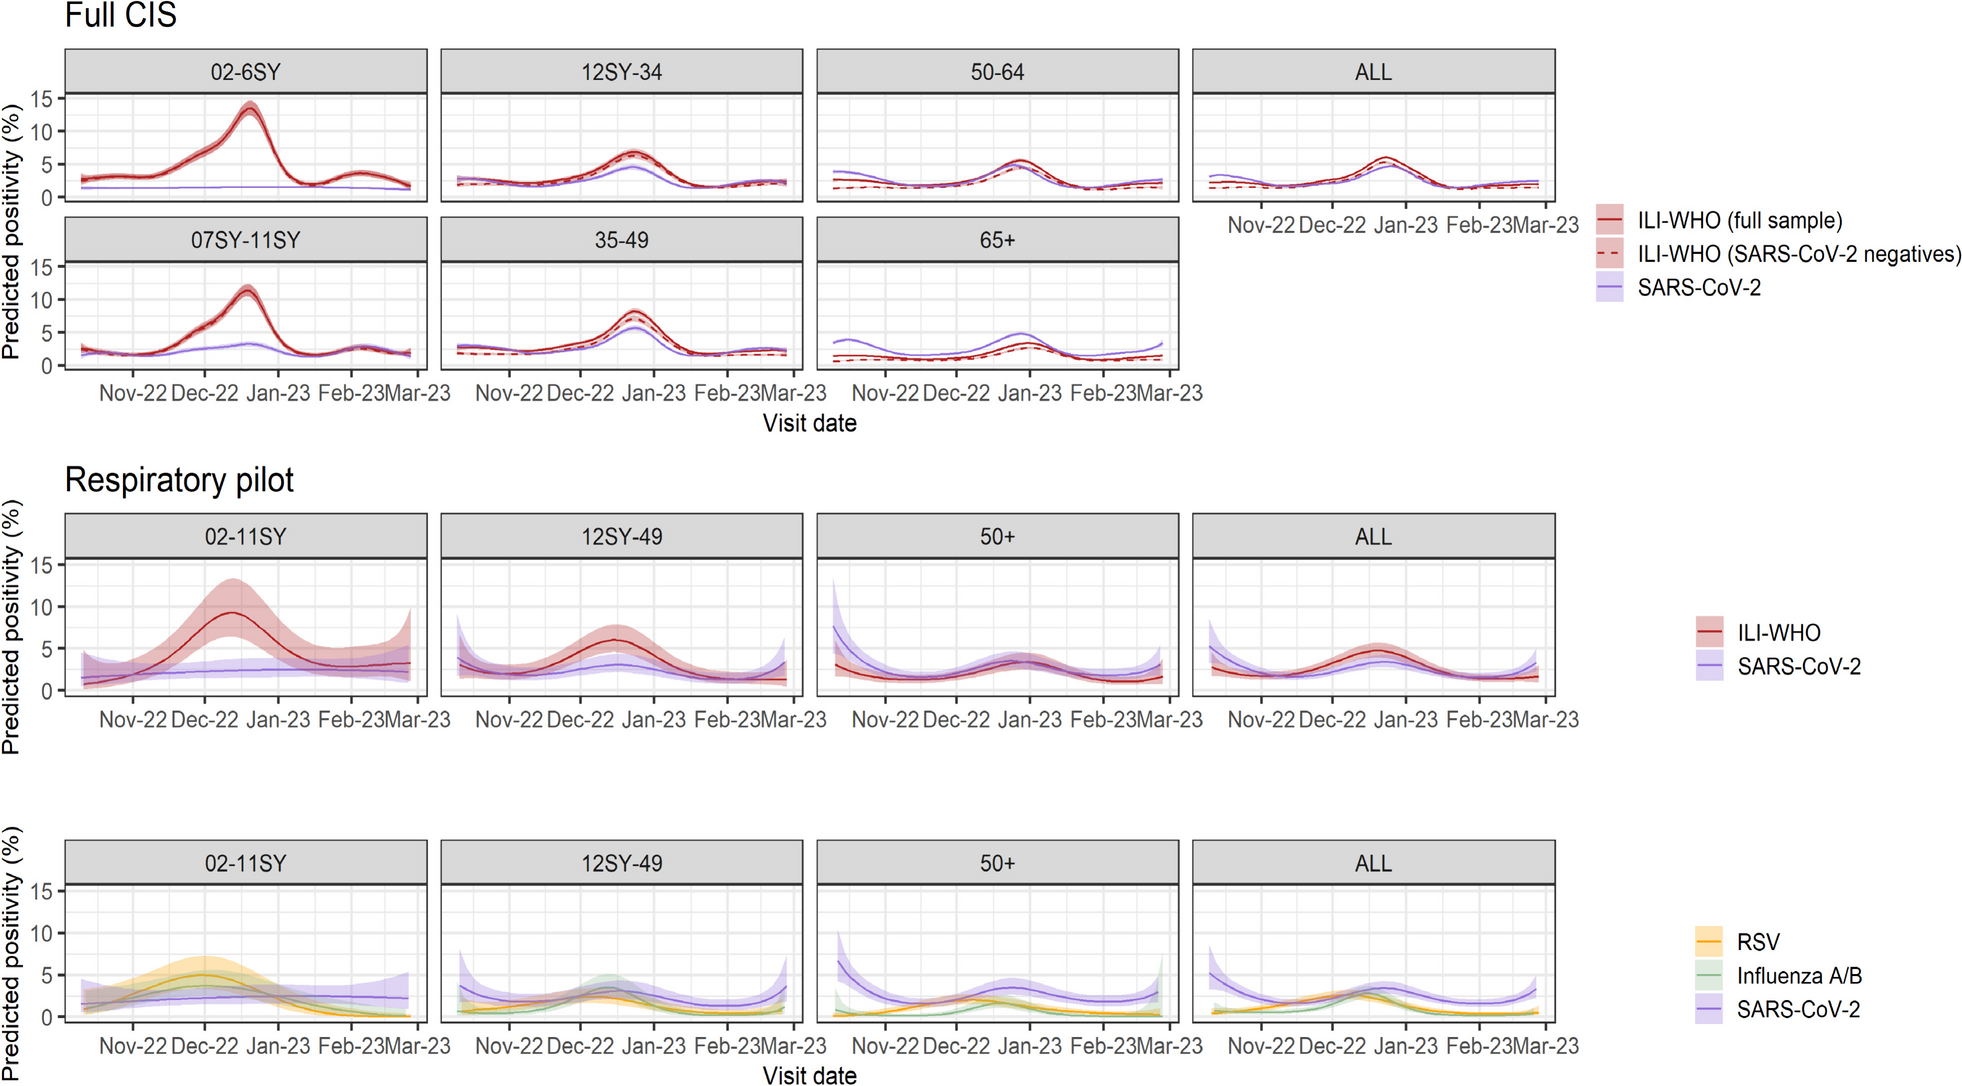
SARS-CoV-2 positivity was notably higher in adults than children, and RSV was more common in children below school year 12 than in older participants. Flu was also less common in participants aged 50 years and above than in younger age groups. By estimating incidence over time using a technique called Richardson-Lucy deconvolution, we found that flu peaks occurred earlier in children than older adults, with a delay of around 2 weeks.
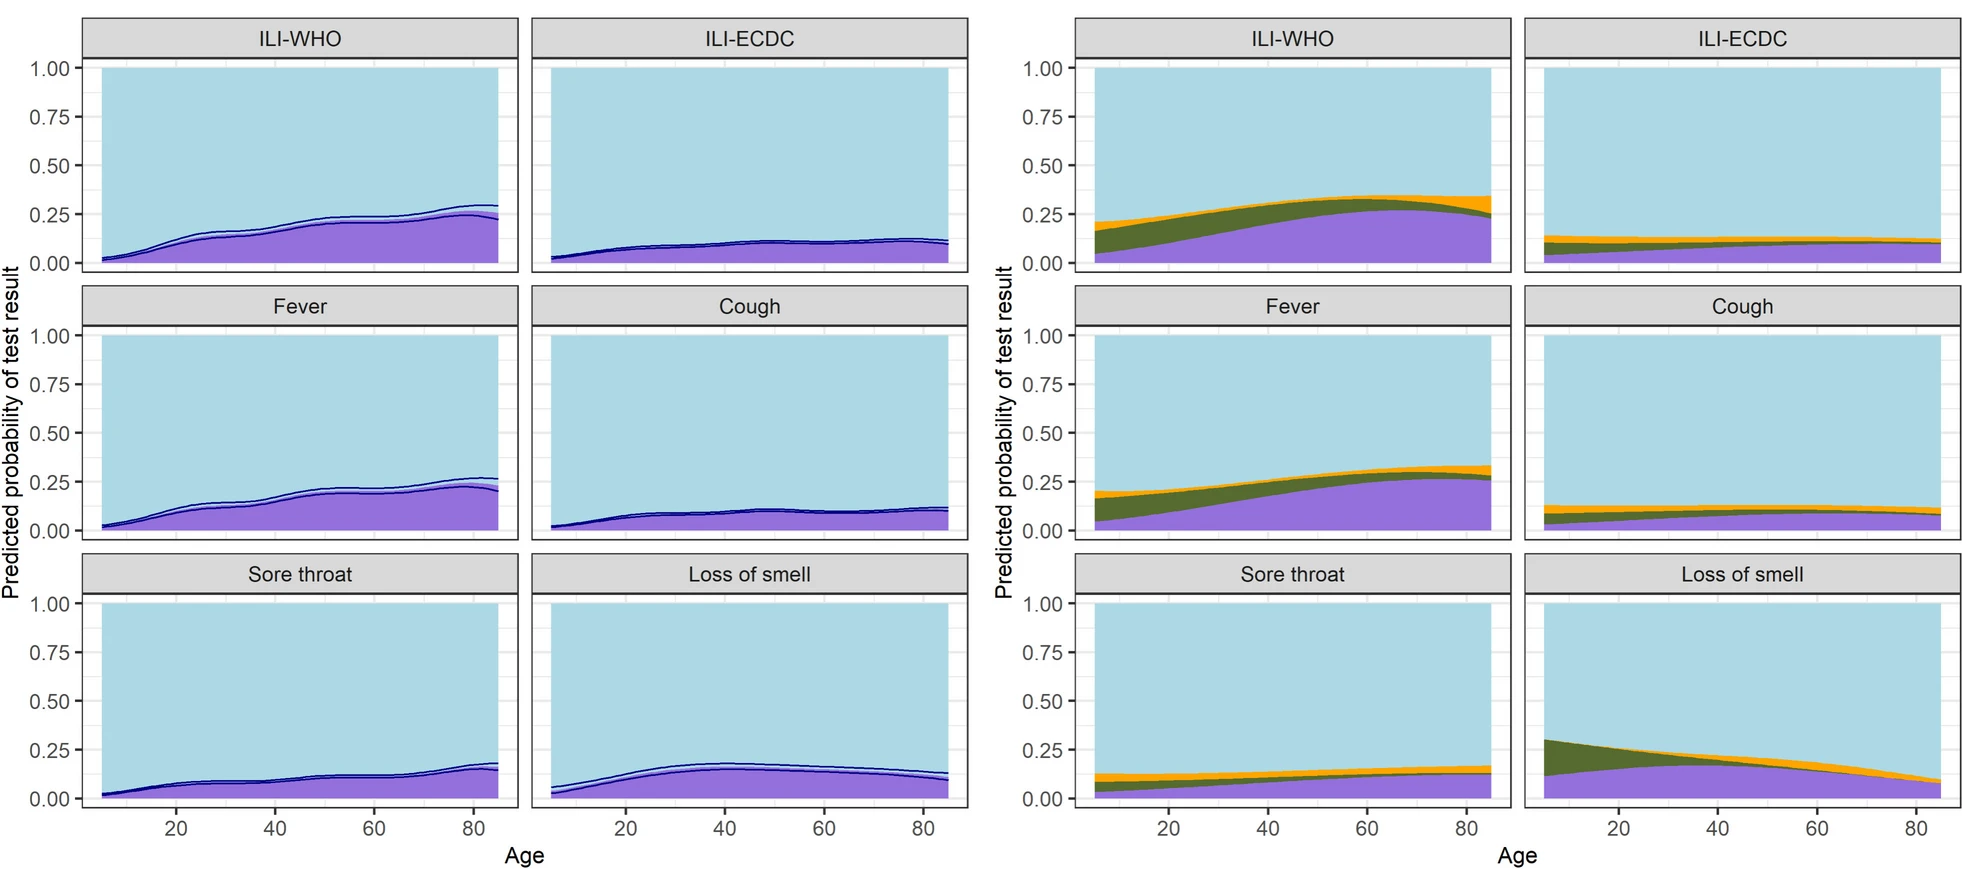
Many of the symptoms reported by people in the survey could not be explained by either of the three viruses we studied, highlighting the role of other infections such as the common cold. Fever was the symptom with the highest percentage of test-positive participants. The likelihood of testing positive for either of the three viruses generally increased by age across symptoms. However, even in older individuals reporting influenza-like-illness as defined by the WHO, only around ~30% had a positive test result for either SARS-CoV-2, the flu, or RSV. We also found that reporting flu vaccination in the past two winter seasons was associated with a lower likelihood of testing positive for flu in the current season.
What are the implications?
Given our findings, further research is needed on the role of other infections such as rhinovirus in causing respiratory symptoms. Future studies would benefit from having more specific data about the onset timing of symptoms and infections. However, our study emphasises the value of community-level data to understanding trends in respiratory infections and symptoms in people outside healthcare settings. Our study also raises important questions about the role of age in infection susceptibility, illness natural history, symptom reporting behaviour, and vulnerability to other symptom-inducing conditions. These questions provide promising avenues for future research, and highlight important considerations to the NHS and public health more broadly.

Follow the Topic
-
BMC Medicine
This journal publishes outstanding and influential research in all areas of clinical practice, translational medicine, medical and health advances, public health, global health, policy, and general topics of interest to the biomedical and sociomedical professional communities.

Related Collections
With Collections, you can get published faster and increase your visibility.
Cardiac immunity and inflammation
BMC Medicine invites submissions to a new Collection focused on the interplay between cardiac immunity and inflammation. We welcome original research, translational studies, and comprehensive reviews that elucidate the underlying mechanisms, clinical consequences, and therapeutic opportunities arising from immune-cardiac interactions. By highlighting the importance of this link, we aim to foster collaboration and advance our understanding of how to improve patient outcomes in heart disease.
The intersection of immunity and cardiovascular biology represents a transformative frontier in modern medicine. Recent studies have highlighted the role of immune responses in various heart conditions, including myocarditis, cardiac xenotransplantation, and heart failure. Inflammation is increasingly recognized as a contributing factor to the pathogenesis and residual risk factor of cardiovascular diseases. This Collection aims to explore the mechanisms by which immune responses influence cardiac function, the role of clonal hematopoiesis and heart disease, and the implications of such interactions for cardiac outcomes.
Understanding cardiac immunity and inflammation is crucial for developing more targeted therapies and accurate CVD risk prediction. Past advances provided insights into the inflammatory processes involving cardiovascular conditions, leading to innovative approaches for diagnosis and treatment. For instance, the identification of biomarkers such as C-reactive protein enhances our ability to assess inflammation in patients with cardiovascular disease. Furthermore, the intersection of cardio-oncology has opened new avenues for research into how cancer therapies influence cardiac immune responses, emphasizing the need for a multidisciplinary approach to patient management.
Continued research in this field holds promise for unveiling drug discovery targets and strategies to mitigate inflammation-related cardiac damage. As we deepen our understanding of the immune mechanisms at play, we may see the development of more clinically relevant models of human disease and precision medicine approaches tailored to individual patients. The integration of this knowledge with advancements in technology, such as biomarker discovery and imaging techniques, could revolutionize the way we approach cardiac care.
Topics of interest include (but are not limited to):
- Role of immunity in cardiovascular biomedicine
- Systemic and cardiac-specific inflammatory pathways
- Residual inflammatory risk, e.g. “SMuRF-less but inflamed”
- Cross-organ communication and immune crosstalk
- Structural and functional cardiac remodeling driven by inflammation
- Novel biomarkers and prediction models
- Clonal hematopoiesis
- Cardio-oncology & therapy-induced immune modulation
- The role of immunity in cardiac xenotransplantation including partial heart transplantation
- Exposome/environmental exposures
- Epigenetic regulation of cardiac immunity and inflammation
- Immune memory and trained immunity in cardiovascular contexts
- Multi-omics integration (epigenomics, transcriptomics, proteomics) in cardiac disease
All manuscripts submitted to this journal, including those submitted to collections and special issues, are assessed in line with our editorial policies and the journal’s peer review process. Reviewers and editors are required to declare competing interests and can be excluded from the peer review process if a competing interest exists.
This Collection supports and amplifies research related to SDG 3 (Good Health and Well Being).
Publishing Model: Open Access
Deadline: Feb 01, 2027
Organoids: connecting molecular insights and clinical practice
BMC Medicine is calling for submissions to our new Collection exploring the use of organoids in connecting molecular insights with clinical practice. We welcome research that investigates their applications in molecular medicine, precision medicine, regenerative medicine, and the understanding of inter-organ crosstalk. Through this Collection, we aim to showcase the transformative potential of organoids in advancing biomedical research and improving patient outcomes.
Organoids, three-dimensional structures derived from stem cells, mimic the architecture and function of real organs, providing a groundbreaking platform for studying human biology and disease. These miniature organs have emerged as powerful tools in biomedical research, enabling scientists to explore complex biological processes, drug responses, and disease mechanisms in a controlled environment. By bridging the gap between traditional 2D cell cultures and in vivo models, organoids offer unprecedented opportunities to investigate cellular interactions, tissue development, and organ-specific functions.
Advancements in organoid technology have been instrumental in enhancing our understanding of various diseases, including but not limited to cancer, neurodegenerative disorders, and infectious diseases. Their capacity for personalized medicine, where patient-specific organoids are used to test drug efficacy, represents a significant leap towards tailored therapies. Furthermore, organoids facilitate the study of inter-organ crosstalk and molecular communication, revealing insights into systemic responses and disease progression that were previously difficult to achieve.
As research in this field continues to grow, we can anticipate innovative applications of organoids in regenerative medicine, the development of novel therapeutic strategies, and the potential for real-time monitoring of disease progression and treatment responses. The integration of multi-organoid systems may also pave the way for more complex models that better reflect human physiology, ultimately transforming clinical practice.
Topics of interest include but are not limited to:
- Organoids in development biology and disease modeling
- Insights into disease mechanisms through organoid models
- Applications of organoids in precision medicine
- Advances in 3D cell culture technologies
- Inter-organ crosstalk and molecular communication
- Organoids in regenerative medicine
All manuscripts submitted to this journal, including those submitted to collections and special issues, are assessed in line with our editorial policies and the journal’s peer review process. Reviewers and editors are required to declare competing interests and can be excluded from the peer review process if a competing interest exists.
Publishing Model: Open Access
Deadline: Nov 17, 2026




